Showing posts with label obamacare. Show all posts

Saturday, July 4, 2015

Politicians, economists and journalists debate the reasons for, and the impact of, proposed sale of Humana to Aetna

By Al Cross
Kentucky Health News

The purchase of Louisville-based Humana Inc. by fellow health-insurance giant Aetna Inc. for $37 billion still needs approval from federal anti-trust officials, partly because of the possibility that the merger will reduce competition and increase premiums.

Some other public officials, the elected kind, wasted no time weighing in on the sale. And, since it deals with health insurance, it may come as no surprise that their statements followed partisan lines, reflecting their views of the Patient Protection and Affordable Care Act.

Wall Street Journal graphic
Even before the deal was announced, Senate Majority Leader Mitch McConnell, R-Ky., said Thursday, "You’ve seen the rumors about Humana being gobbled up by someone who’s even bigger. This kind of government takeover of the private health-insurance market – think of it this way: what Obamacare has basically done is taken the private health insurance market and turned it almost into a regulated utility."

In a press release Friday, McConnell said, "This morning’s announcement, as I predicted during the debate five years ago, is the inevitable result of Obamacare’s push toward consolidation as doctors, hospitals, and insurers merge in response to an ever-growing government."

U.S. Rep. John Yarmuth, D-Louisville, said consolidation in the health-care industry has been going on for decades, "and it is appropriate for the Department of Justice to scrutinize the pending merger to ensure it does not reduce competition, and therefore, consumers' options."

Louisville Mayor Greg Fischer, a Democrat who ran in the primary for McConnell's seat in 2008, said he was "a little surprised by the political nature" of the senator's statement. Fischer and Democratic Gov. Steve Beshear were generally upbeat about the merger. "I am cautiously optimistic that this merger will be a net positive for Louisville and the commonwealth," Beshear said.

Humana has 12,500 employees and 1,500 contractors in the Louisville area. Fischer said, "I think it's very fair to speculate that it will lead to more jobs," and Bruce Broussard, president and CEO of Humana, said, "I think Louisville will be a net beneficiary as a result of this transaction."

However, University of Louisville finance professor David Dubofsky "said it may not turn out so well for the Louisville and Humana employees after all," The Courier-Journal reports, quoting him: "When two companies in the same industry merge, and the acquirer is paying a premium, you have to generate cost savings," partly by reducing employment among workers with similar jobs.

There is a connection between the merger of health-care providers, such as the creation of Kentucky One Health by several hospital groups, and the merger of insurance companies. "Many experts have said that the provider consolidation can drive higher rates—and that more-powerful insurers might have a better chance of countering them and striking pacts for new forms of payment that incentivize efficiency," Anna Wilde Matthews and Christopher Weaver write for The Wall Street Journal.

But they also note, "Research suggests that having fewer insurers leads to higher premiums, said Leemore S. Dafny, a former Federal Trade Commission official who is a professor at Northwestern University’s Kellogg School of Management.

Aetna with Humana would dominate the Medicare Advantage market in some states, with 90 percent of it in Kansas, notes Drew Altman, president of the Kaiser Family Foundation. "Of course, regulators could insist that companies take steps to maintain more competitive markets."

The Journal reports that it analyzed a Medicare database and found, "An Aetna-Humana tie-up would increase by about 180 the number of U.S. counties where at least 75 percent of customers for Medicare Advantage plans are in the hands of a single insurer." Most of those counties are in the South and Midwest. Using another federal database, it found that "In eight states, an Aetna-Humana merger would remove a competitor from the exchanges where individuals can buy coverage under the Affordable Care Act."

The prospect that jobs might be lost in Louisville doesn't mean that the ACA has put financial pressure on Aetna or Humana, Dan Diamond writes for Forbes magazine: "There’s limited evidence that the biggest players are struggling. While the ACA capped insurers’ ability to take profits, industry analysts have been fairly bullish on the sector. . . . And as I wrote earlier this week, the ACA appears to have only helped major insurers, by driving millions of new customers into the market. Aetna and Humana have seen their stock valuations triple in the past five years, since the ACA was signed into law, and the other three major insurers also have seen huge gains."

Diamond also isn't buying the argument, advanced by Aetna officials, that the combined company will be more efficient than the separate ones. "Aetna and Humana already are giant, scaled entities," he notes. "And economists aren’t buying the claim that insurer consolidation will lead to lower costs." As Judy Woodruff noted on "PBS Newshour" Friday, the deal would give the combined company more leverage to negotiate payments to health-care providers.

Health insurers' shares of total Medicare Advantage business
(Kaiser Family Foundation chart)
Diamond says the best case for Aetna's purchase is that it gets the company deeply into the Medicare Advantage business, without having to expend "a great deal of work and time," as Michael Bernstein, a partner at Baird Capital partner who focuses on health care, told Bloomberg News last month. Aetna has only 7 percent of that business, Humana 19 percent -- and about 65 percent of its revenues came from Medicare Advantage plans in 2014, Altman notes. The combined company is expected to get 56 percent of its revenue from government programs.

Diamond says economists see one more possible reason for the merger: "Amid health care’s merger mania, insurers are feeling psychological pressure to make deals of their own." And that does take us back to Obamacare. But the impact on Kentucky has yet to be seen, and so do the reasons.

Friday, July 3, 2015

Ky.'s pro-Obamacare policies led to more enrollment and support for it, but many poor are still uninsured and under-informed

Update: This story was updated to reflect the study's results for those who said they were hurt  by and not directly impacted by the ACA. 

State policy appears to have a major impact on poor people's thinking about the Patient Protection and Affordable Care Act, as well as how they describe their experience with it, according to a Harvard University study published in the journal Health Affairs.

The study surveyed nearly 3,000 low-income residents in three Southern states that had varying approaches to the ACA and its implementation: "Kentucky, which expanded Medicaid, created a successful state marketplace, and supported outreach efforts; Arkansas, which enacted the private option and a federal-state partnership marketplace, but with legislative limitations on outreach; and Texas, which did not expand Medicaid and passed restrictions on navigators" who help people with the federal and state marketplaces.

The survey found that Kentucky, which has enrolled more than 500,000 people in Medicaid and another 109,000 in private health plans through the Kynect health-insurance exchange, had the highest success in application rates, successful enrollments and positive experiences with the ACA, followed by Arkansas and then Texas.

"This corresponds to the general pattern of state-level engagement and support for the ACA coverage expansions in these three states," the researchers write.

The study also found that limited awareness and poor information continue to be two of the greatest barriers to the ACA. Even in Kentucky, where awareness was the highest, only half of the poor people surveyed said they had heard "some" or "a lot" about the ACA's coverage options. About 10 percent of Kentuckians remain without health insurance.

Another barrier to applying for coverage was the perception that it would cost too much, but for those with incomes below 138 percent of poverty in states that have expanded Medicaid, coverage is available without having to pay a premium.

"This adds to previous evidence that information gaps about the law remain a major challenge, particularly among low-income populations who likely have the most to gain from the coverage expansions," the researchers write.

The study also found that application assistance from navigators and others was the strongest predictor of enrollment, increasing enrollment to 93.1 percent from 84.9 percent. Application assistance was most common in Kentucky (46.2 percent) and least common in Texas (31.9 percent). Navigators help consumers choose health-insurance plans to meet their needs and assist them with the application process.

Kentucky reported an overall better application experience than the other two states in the study, and had a significantly higher enrollment rate (92.4 percent) than Arkansas (87 percent) and Texas (84.8 percent).

The study found that advertising about the law didn't seem to affect whether people applied for coverage or enrolled in a plan. However, ads were strongly associated with perceptions of the law.

About 20 percent of respondents said they had read or heard more negative ads and approximately 12 percent recalled more positive ads, and two-thirds said ads were about equal. (Negative ads were most frequently reported in Arkansas, where Obamacare was an issue in a U.S. Senate race last year.)

Twice as many respondents felt that the ACA had helped them as hurt them, although the majority reported no direct impact. In Kentucky, 40 percent said it had helped them, 12 percent said it had hurt them and 48 percent said it had not impacted them directly;  In Arkansas, 30 percent said it had helped them, 17 percent said it had hurt them and 54 percent said it had not impacted them directly; and in Texas, 21 percent said it had helped them, 14 percent said it had hurt them and 66 percent said it had not directly impacted them.

"Nonetheless, 48 to 66 percent of low-income adults in all three states felt the law had not directly impacted them in 2014," the researchers wrote, "which suggests that the ACA has not yet reached many who might benefit from it."

Sunday, June 28, 2015

More dental patients using ERs, showing lack of dental coverage, shortage of dentists and the stepchild status of oral health

More patients are going to hospital emergency rooms for dental care, illustrating how oral health remains the stepchild of the health system despite health-care reform.

"An analysis of the most recent federal data by the American Dental Association shows dental ER visits doubled from 1.1 million in 2000 to 2.2 million in 2012, or one visit every 15 seconds, Laura Ungar reports for The Courier-Journal and USA Today.

Christopher Smith of Jeffersonville, Ind., had a dental
infection that put him in a Louisville hospital for a
week. (Courier-Journal photo by Sam Upshaw Jr.)
"This is something I deal with daily," Dr. George Kushner, director of the oral and maxillofacial surgery program at the University of Louisville, told Ungar. "People still die from their teeth in the U.S."

A longstanding federal law requires ERs to treat patients regardless of their ability to pay. "Although they often provide little more than painkillers and antibiotics to dental patients, the visits cost more than three times as much as a routine dental visit, averaging $749 if the patient isn't hospitalized — and costing the U.S. health care system $1.6 billion a year," Ungar reports.

Private dental insurance is not common. "Just over a third of working-age adults nationally, and 64 percent of seniors, lacked dental coverage of any kind in 2012, meaning they had to pay for everything out of pocket," Ungar writes. The Patient Protection and Affordable Care Act "requires health plans to cover dental services for children but not adults," and "Medicare generally doesn't cover dental care at all," she notes.

In Kentucky, the expansion of Medicaid under Obamacare has increased dental visits in the program by 37 percent, but it offers "only a short list of dental services," such as extractions, which patients often choose instead of restorative work, for which they would have to pay.

Another big issue is that many dentists don't accept Medicaid, which pays them only 41 percent of private reimbursement, Ungar reports. Also, Kentucky has a shortage of dentists. "A 2013 workforce study by Deloitte Consulting found the state needs 612 more to meet demand," Ungar notes.

More dentists would encourage more preventive treatment, which dentists say would save a lot of money. "If we were going to the dentist more often, we could avoid a lot of this," Dr. Ruchi Sahota, a California dentist and consumer adviser for the ADA, told Ungar. "Prevention is priceless."

Fewer than 60 percent of Kentuckians saw a dentist in 2013, making their dental-visit frequency 43rd in the nation, according to the Kentucky Health Issues Poll.

Thursday, June 25, 2015

Supreme Court upholds Obamacare subsides in all states; ruling has no direct effect on Kentucky, but focuses political debate

By Molly Burchett
Kentucky Health News

The U.S. Supreme Court ruled Thursday that the tax subsidies provided under the Patient Protection and Affordable Care Act are legal in every state.

While the ruling has no effect on Kentucky, and would have had no direct effect if it had gone the other way, it sets the table for continued political debate about health policy in Congress and in Kentucky's race for governor.

"Congress passed the Affordable Care Act to improve health insurance markets, not to destroy them," Chief Justice John Roberts wrote in the 6-3 majority opinion. "If at all possible, we must interpret the Act in a way that is consistent with the former, and avoids the latter."

The law says the federal government can pay subsidies to help people afford insurance bought through “an Exchange established by the State.” The lawsuit argued that Americans in the 34 states using the federal exchanges were not eligible for the subsidies, which are crucial to the law's success, helping to make health insurance more affordable, reducing the number of uninsured Americans. Proponents of the law say not providing subsidies to individuals in those 34 states relying on the federal exchange would have upended the law, notes CNN.

President Obama called on critics to accept the law as permanent, saying after the ruling, "The Affordable Care Act is here to stay."

But Senate Majority Leader Mitch McConnell, R-Ky., called Obamacare “a rolling disaster for the American people,” with a “multitude of broken promises, including the one that resulted in millions of Americans losing the coverage they had and wanted to keep. Today’s ruling won’t change the skyrocketing costs in premiums, deductibles, and co-pays that have hit the middle class so hard over the last few years.”

Maps: Percentage uninsured in 2012, above, and 2014, below
Obama countered, "The setbacks I remember clearly. But as the dust has settled, there can be no doubt that this law is working. It has changed, and in some cases saved, American lives. It set this country on a smarter, stronger course." He added, "The law has helped hold the price of health care to its slowest growth in 50 years" and "Nearly one in three Americans who was uninsured a few years ago is insured today. The uninsured rate in America is the lowest since we began to keep records."

A White House fact sheet noted that the law also expanded "access to preventive care, including immunizations, well-child visits, certain cancer screenings, and contraceptive services, with no additional out-of-pocket costs as well as no more annual caps on essential benefit coverage and new annual limits on out-of-pocket costs."

Since Kentucky established its own exchange, Kynect, for buying subsidized health insurance or signing up for Medicaid, the ruling may seem moot for Kentuckians. However, it establishes some of the facts for a health-care policy debate in the governor's race between Republican Matt Bevin and Democratic Attorney General Jack Conway.

The exchanges and the expansion of the federal-state Medicaid program are choices for the states, and Bevin has said that if elected he would shut down Kynect and end the Medicaid expansion, which has covered about 430,000 Kentuckians. The federal government is paying their entire cost through next year; in 2017 the state would start picking up a small share, rising to the law's limit of 10 percent in 2020.

Conway has acknowledged questions about whether the state can afford to pay its share, but to “say you’re going to kick a half a million people off of health insurance based on what we may or may not be able to afford in 2021 is irresponsible.” A Conway spokesman said he "appreciates the court's careful consideration of this case and agrees with today's decision," reports the Lexington Herald-Leader.

The Herald-Leader's Mary Meehan interviewed officials and experts for a package of questions and answers about the law and Kentucky. It is published at http://www.kentucky.com/2015/06/25/3917832_in-light-of-the-supreme-court.html.

Outgoing Gov. Steve Beshear, a Democrat who expanded Medicaid, said in a statement that the decision “reaffirms that, from the very start, we did the right thing for the more than 500,000 Kentuckians who have qualified for health-care coverage through Kynect since January 1, 2014.”

Susan Zepeda, president and CEO of the Foundation for a Healthy Kentucky, said in a release, "While many have been awaiting this important decision, we must remember that much remains to be done to assure that all Kentuckians – and all Americans – have timely access to safe, effective and affordable quality care." Zepeda said Kentuckians continue to work on ways to improve and protect Kentuckians' health, such as reforming the way we pay for care and making health care cost and pricing more transparent.

"As people who have forgone care too long because of its expense now gain access to care, it will place a larger short-term burden on the health-care system, which approaches like these can help to address," said Zepeda. "The Affordable Care Act permits – and incentivizes – local health care innovation. We can and must shape Kentucky solutions to Kentucky’s health challenges."

Aetna is close to a deal to buy Humana, Bloomberg reports

Getty Images, via CNBC
Health insurer Aetna "is said to be closing in on a deal to buy" Louisville-based Humana Inc., Julie Hyman reports for Bloomberg News, "and a deal could come "as soon as this weekend."

Humana is also expecting an offer from Cigna Inc., but Humana's board of directors "prefers the Aetna offer," Hyman reports, citing unnamed people familiar with the negotiations. The deal has been discussed for weeks, but Aetna didn't make a formal proposal until this week.

The last major obstacle to a deal may have been the Supreme Court's ruling today that people in all states are entitled to tax subsidies for health insurance under the Patient Protection and Affordable Care Act, Hyman suggests, noting higher stock prices for health-insurance companies.

"Shares of Humana rallied more than 8 percent after trading was briefly halted for volatility," Reem Nasr of CNBC reports.

Humana is an attractive buy because "a great deal of its business — 73 percent of its premiums revenue — comes from contracts with the federal government," David Mann reports for Louisville Business First. "That means Humana is flush with Medicare business, which is a fast-growing category in the industry as many baby boomers are reaching the eligibility age. Its competitors, including Aetna, don't have nearly as much of this business."

"Consolidation among the country's top insurers follows a massive consolidation among providers in pharmacy, hospital and patient care, which has increased the leverage against insurers like Humana and Aetna," Grace Schneider reports for The Courier-Journal.

Sunday, June 21, 2015

Kentucky is cracking down on Suboxone, a heroin substitute that has become a big part of the illegal trade in painkillers

A drug that was supposed to help people get off heroin has "created a new cash-for-pills market and a street trade" that state officials are trying to stop, Mary Meehan reports for the Lexington Herald-Leader.

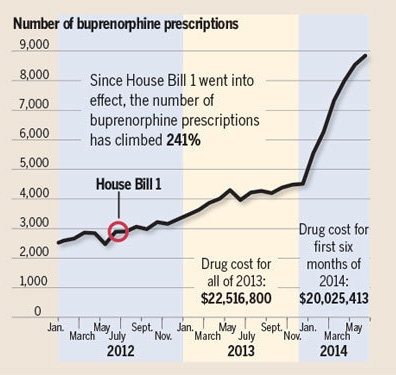
The drug is buprenorphine, the active ingredient in the brand-name drugs Suboxone and Subutex, which became more popular in 2012, when the state cracked down on "pill mills" that were freely handing out prescriptions for painkillers. "A lot of the pill mills morphed into facilities that dispense these prescriptions," Dr. John Langefeld, medical director for the state's Medicaid program, told Meehan.

Also, Meehan writes, the Patient Protection and Affordable Care Act required insurance plans to cover treatment for substance abuse, and "as more Medicaid patients and others got health-insurance coverage, more people obtained prescriptions for buprenorphine, Langefeld said. . . . According to a state report, one user obtained prescriptions from nine doctors."
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Lexington Herald-Leader chart by Chris Ware from state data
Use of the drug in Kentucky "has increased 241 percent since 2012," Meehan reports. "And 80 percent of the prescriptions for it were being written by 20 percent of the state's 470 certified prescribers, said Dr. Allen Brenzel, medical director of the state's Department of Behavioral Health. . . . Since 2011, 10 doctors have been sanctioned by the Kentucky Board of Medical Licensure because of problems prescribing Suboxone."

Suboxone is supposed to be taken in conjunction with therapy and drug testing. "a patient receives a controlled dose of a legal drug as the dose is tapered by a physician for a safe and effective withdrawal," Meehan notes. However, "doctors started to see Suboxone patients on a cash basis, asking for as much as $300 for an office visit that included a prescription for the maximum allowable amount of Suboxone. Patients often received no therapy or drug testing. Some patients were on the maximum dose indefinitely, Brenzel said." Some doctors prescribed the drug with other painkillers, creating an illegal market.

To prevent such abuse by unscrupulous doctors, the medical-licensure board has issued regulations that require "more physician education and the requirement that the drug be prescribed only for medically supervised withdrawal and not be given to pregnant women," Meehan writes. "Patients should also be closely monitored and drug tested. If those rules are not followed, a doctor can face sanctions or restrictions to his medical license."

Suboxone was in the national news recently because the accused killer in the Charleston, S.C., shootings was arrested for illegal possession of it four months ago at a South Carolina shopping mall, the Herald-Leader notes.
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Sunday, May 17, 2015

Lexington Herald-Leader says Kentucky Hospital Association report on members' finances damages the group's credibility

The Kentucky Hospital Association's recent "Code Blue" report on its members' finances is a symptom of "financial hypochondria," the Lexington Herald-Leader said in a long editorial Sunday. It said the title, "signaling a patient needs resuscitation, is an unintentionally fitting title because the KHA's credibility could use a little CPR."

Read more here: http://www.kentucky.com/2015/05/17/3855678/hospitals-suffering-financial.html#storylink=cpy

The report "voices a universal human desire: more money, less accountability. The association implies that federal financial penalties aimed at reducing harm to patients are too onerous for hospitals that care for Kentuckians," the editorial says. "Little more than anecdotes are offered with no acknowledgment that some Kentucky hospitals are recording record bottom lines and steep drops in uncompensated care."

The newspaper offered its own anecdote, a large one, noting that the University of Kentucky's medical center is a major beneficiary of the Medicaid expansion under federal health reform: "The 2014 period saw an 83 percent drop in non-paying inpatients, a 66 percent drop in non-paying outpatients and a $60 million increase in Medicaid revenue. UK Healthcare's annual net income through March is up $70 million over the same time last year. Not all of that increase is due to the Medicaid expansion or Kynect," the state exchange for enrolling in Medicaid or buying private insurance.

"The important point," the paper says, is that "Slowing down spending on hospital care is one of the best things we can do for the economy and our health. The United States spends the highest percentage of its GDP on health care of any country but gets worse outcomes. Even by U.S. standards, Kentuckians over-utilize hospital care."

Read more here: http://www.kentucky.com/2015/05/17/3855678/hospitals-suffering-financial.html#storylink=cpy

Friday, May 15, 2015

3,047 got private health insurance in special March-April signup designed to avoid or reduce tax penalty for not being covered

More than 3,000 Kentuckians signed up for health coverage during a special March-April enrollment period that allowed them to avoid or reduce tax penalties for being uninsured.

"At the Feb. 15 close of the 2015 open enrollment period, 158,685 individuals had enrolled in health care coverage through Kynect for 2015," a state press release said. "That number included 102,830 Kentuckians who have either newly enrolled in a qualified health plan since Nov. 15, 2014, or renewed the private insurance plan they purchased through Kynect last year."

With the additional 3,047 enrollments, the final enrollment in private health insurance was 105,877. The federal tax penalty for being uninsured in 2014 was $95 for each adult household member or 1 percent of income, whichever is greater. In 2015, it will be $325 for each adult or two percent of income, whichever is greater. Penalties for not insuring children are half those for adults.

“Given that the personal risks of not having health coverage are even greater than the penalties, we decided to continue a special enrollment period to allow those individuals more time to sign up,” Gov. Steve Beshear said in the release.

Those who took advantage of the special enrollment period will still owe a penalty for any months they were uninsured and did not qualify for an exemption in 2014 and 2015. "This special enrollment period was designed to allow such individuals the opportunity to get covered for the remainder of the year and avoid additional fees for 2015," the release said.

Sunday, May 10, 2015

Kentucky hospitals say they're losing money on Obamacare, as cost of treating new Medicaid patients exceeds reimbursements

By Melissa Patrick
Kentucky Health News

Kentucky hospitals are struggling financially because of the billions of dollars in cuts caused by the implementation of the Patient Protection and Affordable Care Act, and many aren't sure they will survive, the Kentucky Hospital Association said at its annual meeting May 8.

KHA applauded the successful implementation of the federal health reform in Kentucky, which has extended health insurance coverage to approximately 500,000 more Kentuckians, mainly through expansion of Medicaid, but said that has come at a "significant cost to our commonwealth hospitals."

"The expansion [of Medicaid] has infused money into some of our hospitals, which is good, but the rest of the story is the cuts," KHA President Michael Rust said.

KHA Chair Dennis Johnson, CEO of Hardin Memorial Health in Elizabethtown, said  the revenue from the expansion "is less than the cuts Kentucky hospitals will experience in order to finance the ACA."

Kevin Halter, KHA's incoming chair and CEO of Our Lady of Bellefonte Hospital in Ashland, said,
“Much has been made about the fact that Kentucky hospitals have received an additional $506 million in Medicaid payments last year through the expansion, suggesting that hospitals' bottom lines are healthier as a result, but what is often not mentioned is that hospitals lose money on every Medicaid patient they treat.”

The report says that changes in the way hospitals are paid under Obamacare are projected to result in the loss of almost $7 billion in federal cuts to Kentucky hospitals through 2024:

  • Lower-than-cost Medicaid and Medicare reimbursements, 82 percent and 86 percent respectively, with actual Medicaid and Medicare payment cuts from 2010 to 2024 projected to be $4.6 billion
  • Readmission penalties, which can be as much as 3 percent of Medicare payments, imposed on hospitals that readmit patients within 30 days of discharge, regardless of the reason
  • Medicare cuts to hospitals that have any increase in hospital-acquired infections
  • Cuts, delayed until 2017, in extra payments to hospitals that have a "disproportionate share" of Medicare and Medicaid patients.

KHA also cited impacts that aren't associated with the reform law, such as sequestration, or automatic across-the-board federal budget cuts, and other cuts in Medicare.

Hospital officials said that rural hospitals have been hit hardest by these changes because 72 percent of their patients are on Medicaid or Medicare. A recent report by state Auditor Adam Edelen found that 68 percent of Kentucky's rural hospitals have below-average of poor financial health, with 34 percent of the total in the latter classification.

Part of the problem is that the law was built on the nationwide presumption that about half of the newly insured would have private health insurance and the other half Medicaid, but in Kentucky, a poor state, 75 percent of the newly insured are covered by the Medicaid expansion, which covers those earning less than 138 percent of the federal poverty line, or about $33,000 for a family of four.

Halter said while hospitals got $506 million for treating patients covered by the expansion, that treatment costs the hospitals $617 million to deliver that care. While low Medicaid reimbursement is not a new problem, Johnson said, "There's no question it's been accelerated under the ACA."

Gov. Steve Beshear said expanded Medicaid payments had "blunted the impact of other fiscal pressures on hospitals. . . . We are very aware of the challenges that medical providers face in Kentucky. Rather than trying to turn back the clock and return to old business practices, we are working directly with providers to help them develop new strategies for better, more efficient, quality health care delivery."

The challenges are real.

A September 2014 survey found that more than 65 percent of the 109 responding Kentucky hospitals had reduced staff since June 2013, eliminating more than 7,700 positions, with more jobs lost in rural hospitals than the urban ones. About 44 percent had frozen or reduced wages, and 40 percent of had cut costs by reducing or eliminating programs, such as closing psychiatric units and outpatient clinics.

"The reality is that hospitals are being forced to reduce costs to deal with these financial pressures," said Charles Lovell, CEO Caldwell Medical Center in Princeton. "This is the third year without our employees getting an increase."

While Obamacare has reduced hospitals' losses on patients who can't pay, Halter noted that 12 percent of Kentuckians remain uninsured, and the report said hospital emergency rooms are still the first choice for many new Medicaid patients because they have't found a regular physician. Many Kentucky counties are short of doctors.

Sunday, April 12, 2015

As income taxes are filed, half who got Obamacare subsidy will have to pay part of it back; almost as many will get a refund

By Melissa Patrick
Kentucky Health News

This week will go down in history as the first time the Internal Revenue Service enforced the Patient Protection and Affordable Care Act's tax penalty for those who can afford insurance but didn't buy it.

The penalty for those who don't qualify for an exemption is $95 per adult and $47.50 per child, or 1 percent of your income, whichever is larger. The penalty will increase next year to the greater of $325 per adult or 2 percent of household income.

"Ever since its passage, the mandate that every American have health insurance has been at the heart of the controversy over the ACA," Elaine Kamarck writes for the Brookings Institution. It was an issue long before the law passed; in the 2008 presidential primaries, Hillary Clinton favored it and Barack Obama opposed it; as president, he changed his mind.

Tens of thousands of Kentuckians who got subsidies to help pay for their health insurance through the Kynect exchange will probably be surprised to find that they will have to repay some of the subsidy, or that they will get a refund, depending on the difference in their actual income level and the income that was recorded at the time they bought insurance. Most incomes were likely based on an estimated income for the year. Generally, if you overestimated your 2014 income, you will get a refund. If you underestimated it, you will have to repay some or all of the subsidy, which was subtracted from the "sticker price" of insurance to calculate your premium.

Infographic from Kaiser Family Foundation
A study by the Kaiser Family Foundation estimates that 50 percent of Americans who got 2014 tax subsidy will owe some money, and 45 percent will receive a refund. The foundation estimates the average repayment will be $794 and the estimated average refund to be $773.

Some reasons for the income differences are getting a raise, losing a job, and working a different number of hours; and non-job factors such as a change in family size as a result of births, deaths or divorce. These changes should be reported when they occur, so subsidies can be modified, but often aren't, says the Kaiser Family Foundation.

John Ydstie of NPR reports some real examples of policyholders facing these surprises. He tells the story of one person who makes $30,000 a year who decided to take less than her estimated $250-a-month premium subsidy because of her uncertainty about the program, and is getting a $3,900 refund. He notes that most people on Obamacare can't afford to do this.

Ydstie also tells the story of a young woman whose monthly subsidy dropped to $60 from $250 after she married her longtime partner in 2014 and their combined incomes bumped them into a different category. They have to pay back $1,800 but are hoping the amount will be adjusted to $400, to apply only to the months they were married; this has not yet been determined.

As the IRS implements the law, it is faced with budget, staffing, and operational cuts, Kamarck writes: "Given the staff limitations of the IRS and the complexity of reporting and reconciling the government subsidies in the law with people’s income there is likely to be confusion, frustration and, most importantly, a lot of people who find out that their tax refund is a great deal smaller than they anticipated." She suggests that the IRS, in order to survive the first tax season with the ACA, "give taxpayers a break whenever it can."

Sunday, April 5, 2015

New diabetes cases in expanded-Medicaid states much higher than other states; 46,000 new Ky. Medicaid clients got screened

By Melissa Patrick
Kentucky Health News

New diabetes cases among poor Americans are much more numerous in Kentucky and other states that have embraced the Patient Protection and Affordable Care Act, a medical testing company has found. The diagnoses rose 23 percent in the Obamacare states and barely rose in the others, apparently because state Medicaid programs are encouraging screening for diabetes.

Quest Diagnostics conducted the study by analyzing laboratory test results from all 50 states and the District of Columbia in its large database over two six-month periods, Sabrina Tavernise reports for The New York Times. The authors determined that because in January 2014, 26 states and the District of Columbia had expanded Medicaid and 24 had not, it was a good time to conduct this study, which is reported in the journal Diabetes Care.

The research team used the results of the basic test for diabetes, which measures a form of hemoglobin that has interacted with glucose, A1c. "In the states that expanded Medicaid, the number of Medicaid enrollees with newly identified diabetes rose by 23 percent, to 18,020 in the first six months of 2014, from 14,625 in the same period in 2013," Tavernise reports. "The diagnosis rose by only 0.4 percent — to 11,653 from 11,612 — in the states that did not expand Medicaid."

A Kentucky study indicates that more screening isn't the only reason for such numbers; the Medicaid expansion population appears to be more susceptible to diabetes than normal.

The study by Deloitte Consulting found that chronic conditions, including diabetes, were more than twice as prevalent in the expansion population than other people of the same age and gender who were on Medicaid before it expanded. That comparative group was considered to be the group most similar to the Medicaid expansion population, since the state lacks historical data for the expansion group.

The study found that the Medicaid expansion group had a 102.5 percent higher prevalence of diabetes than the comparative group. About two of every 1,000 in the expansion group had diabetes, compared to one of every 1,000 members of the traditional-Medicaid group.

About 46,000 of the 400,000 people in the expansion group had a diabetes screening in the first year of the expansion. Both studies suggest better access and utilization of preventive care and early diagnosis will promote earlier treatment and better long-term outcomes.

Kentucky ranks 17th among the states in prevalence of diabetes, according to the 2014 "States of Obesity" report.  The state Cabinet for Health and Family Services reports an estimated 233,000 adult Kentuckians have pre-diabetes. For county-by-county data on diabetes, click here.

Quest Diagnostics recognized that its study only looked at changes in raw numbers of the lab results from one company and did not have access to a federal data set. This has caused some to voice skepticism that the study results are a result of the Medicaid expansion. Others, while recognizing that the study did not "have the precision of a scientific drug trial," Tavernise writes, said "the changes in the numbers are real ... 23 percent versus zero," and that "the health-care law was the most plausible explanation for the findings." Another said, "for an observational study, it’s really very strong."

Kentucky Health News is an independent news service of the Institute for Rural Journalism and Community Issues, based in the School of Journalism and Telecommunications at the University of Kentucky, with support from the Foundation for a Healthy Kentucky.

Auditor will hold meetings in Prestonsburg, Princeton and Sonerset to discuss his report on financial status of rural hospitals

State Auditor Adam Edelen will hold three public meetings in rural communities to discuss the findings of his special report about the financial health of rural hospitals.

The meetings will be held Monday, April 21 at 1 p.m. at the Mountain Arts Center in Prestonsburg; Monday, May 4 at 11 a.m. (CT) at the Caldwell County Memorial Hospital in Princeton; and Thursday, May 6 at 1 p.m. at the Liberty center of Somerset Community College.

The report, which covers fiscal years 2011 through 2013, found that as many as one-third of Kentucky's rural hospitals were in poor financial shape, with 68 percent of them ranking below the national average financially.

“Although closure may be an unfortunate reality for some," Edelen said in the press conference, "I believe more can and should be done to help these hospitals rethink their models of business in delivering health care in the 21st century." He went on to suggest rural hospitals consider hiring outside managers, merge with larger hospitals, form coalitions with other rural hospitals or find a specialized health niche as possible alternate business models to consider.

The report calls for the creation of a state work group to monitor rural hospitals, including making sure state law gives them the flexibility to retool their business models. Susan Zepeda, president and CEO of the Foundation for a Healthy Kentucky, suggested that the proposed work "could be incorporated into the work already under way under a State Innovation Model grant, which is engaging many sectors of health service in Kentucky in an ambitious, collaborative redesign effort."

Edelen said some of the primary problems faced by rural hospitals stem from the many changes in health care since the inception of Medicaid managed care, a decrease in the number of health-care providers, and an economic climate in some areas that doesn't support the current health payment model, which depends on the majority of its users to have private health insurance.

The report suggested that the Cabinet for Health and Family Services negotiate better contracts with managed-care organizations as it approaches the June 30 deadline, especially to address provider payments, stricter penalties for non-compliance and increased administrative burdens that managed care has put on hospitals. Edelen and Haynes sounded hopeful that this was going to happen.

Gov. Steve Beshear called Edelen's report "a dated snapshot" because the 2013 data used in the report does not include 2014 information,when the federal health reform was fully implemented through expansion of Medicaid to people with incomes up to 138 percent of the federal poverty line. Beshear said hospitals received $506 million to care for such people in 2014 while seeing significant reductions in losses on patients who couldn't or wouldn't pay.

Edelen's spokeswoman, Stephenie Hoelscher, said in an email that Edelen believes the full effect of all the changes in health care to hospitals' bottom line is still not clear, and his report establishes a baseline for critical analysis going forward.

Monday, March 30, 2015

Up to 1/3 of rural hospitals in poor financial shape, auditor finds, calling report a baseline for local decisions that could be tough

By Melissa Patrick and Al Cross
Kentucky Health News
For a video of Edelen's press conference, click here. For a cn|2 report with video, go here.

FRANKFORT, Ky. -- As many as one-third of Kentucky's rural hospitals are in poor financial shape, and the survival of some will likely depend on their willingness to adopt new business models, state Auditor Adam Edelen said Monday.

Unveiling a nine-month study, Edelen said 15 of the 44 hospitals examined were in "poor financial health," and warned, "Closure may be an unfortunate reality for some."
Rural hospitals in purple declined to make useful financial information available to the auditor's office.
The study did not include 22 of the 66 Kentucky hospitals that are located outside metropolitan areas, which declined to participate or didn't provide the type of information requested. Edelen said those hospitals are mainly privately owned. If they had been included, Kentucky Hospital Association CEO Michael Rust said, the financial picture "would be better, but I don't think they would be substantially different."

Gov. Steve Beshear said the report was "a dated snapshot" because its most recent data was from 2013, before federal health reform was fully implemented. "Conditions are no longer the same," Beshear said in a news release. "Hospitals received more than $506 million in 2014 through new Medicaid expansion payments, while seeing significant reductions in uncompensated care costs.  Those are huge changes to hospitals’ bottom lines that are not shown here."

Edelen, who was Beshear's first chief of staff, said the full effect of federal health reform isn't certain. His report noted that Kentucky hospitals have had higher-than-average penalties from Medicare for readmitting patients within 30 days, a newly implemented feature of the law. Forty of the 63 hospitals penalized were rural, and nine of the 39 in the U.S. that got the maximum penalty were in Kentucky.

"This report doesn't speak to causation" by the reform law or the state's relatively new managed-care system for Medicaid, Edelen said, it is "not a rebuke" of either, but provides "a baseline for monitoring" by policymakers at the state and local levels.

The report says that to survive, rural hospitals must adapt to new business models, such as merging with larger hospitals or hiring them as managers, forming coalitions with other rural hospitals, or finding a health-care niche that hasn't been served.

Edelen cited Rockcastle Regional Hospital, which has become a niche provider of ventilator dependent care and the coalition formed by Morehead's St. Claire Regional Medical Center and Highlands Regional Hospital in Paintsville to provide more efficient care, improve patient access and adapt to changes under the reform law.

Adaptations might be a hard pill to swallow for many rural hospitals because they call for yet more change in the rapidly changing health-care landscape of electronic health records, managed care, Medicaid expansion and full implementation of the Patient Protection and Affordable Care Act.

Edelen said adaptation is important for rural communities, for whom "the importance of rural hospitals cannot be understated. They provide health care to 45 percent of Kentuckians and in every community they serve they act as one of the larger employers, paying a significantly higher wage than the average the community experiences."

He also cited the many small hospitals that have formed relationships with larger networks to relieve the increased administrative burden associated with the three-year-old managed-care system. The report says half the hospitals studied have reported an increase in hours spent on administration.

The report suggested that the state Cabinet for Health and Family Services negotiate better contracts with managed-care organizations, partly to streamline MCO rules and paperwork to reduce the administrative burden. "We are optimistic that the current work of the cabinet to improve those contracts is going to bear real fruit," Edelen said.

The new contracts will start July 1. In an interview, cabinet Secretary Audrey Haynes sounded optimistic about them but said she couldn't give details.

Haynes has been saying since she became secretary three years ago that many hospitals must change the way they do business. She said in an interview that the readmission penalties have forced hospitals to change by providing better discharge planning, and utilizing outpatient services like home health, nursing homes and rehabilitation.

One Kentucky hospital, in Nicholas County, has closed in the last year. Haynes said the cabinet is working with Fulton County, whose hospital is scheduled to close March 31, to explore how to continue providing care at the facility, such as an emergency room or an ambulatory surgical center.

Haynes recommended in the interview that all nonprofit hospitals put audited financial records and their tax returns on their websites and adhere to open-meeting laws.

In a lengthy response, included in the report, Haynes rejected Edelen's suggestion that her cabinet regularly monitor the fiscal strength of rural hospitals. She said in the interview that would pose a conflict of interest, since the cabinet regulates the hospitals.

Edelen's analysis of hospitals' financial health was based on percentage of revenue kept as profit, number of days of cash on hand, debt financing and depreciation. It found that the financial condition of 68 percent of Kentucky’s rural hospitals scored below the national average.

Edelen's office also surveyed rural hospital administrators, held 11 public hearings and met with representatives of all five Medicaid managed-care companies. His report found that:
  • Rural hospitals that were geographically well-positioned, such as Pikeville Medical Center, scored high while geographically-isolated hospitals, like those in Clinton and Wayne counties, scored low. The Clinton County Hospital is in bankruptcy to restructure debt incurred for an expansion and modernization.
  • The Pikeville hospital, formerly Pikeville Methodist, was one of only three judged to be in excellent financial health. The others were critical-access hospitals in Franklin and Morganfield.
  • Critical-access hospitals, which limit their beds, services and patient stays to qualify for federal reimbursement at 101 percent of cost, scored better than regular acute-care hospitals. They accounted for seven of the 14 that were above the national average and thus were rated "good."
  • Fifteen hospitals were rated "fair" and 15 were rated "poor." Westlake Regional Hospital in Columbia, which is in bankruptcy, was at the bottom, far worse than the next highest, St. Joseph Mount Sterling.
  • The number of health-care providers across the state – particularly in rural Kentucky – dropped significantly between 2013 and 2014. The cabinet disputed that finding, based on different measurements.
Here are the rankings (click on the image for a slightly larger version):

Sunday, March 29, 2015

Washington Post columnist looks at data, talks to experts and concludes Obamacare is working, at less cost than expected

The federal health-reform law "has accomplished its goal of expanding coverage — at a significantly lower cost than expected," columnist Ruth Marcus writes for The Washington Post "after talking to numerous health-care experts and examining the data."

Marcus writes up front, "There is a legitimate ideological debate about whether it is a wise use of federal power to require individuals to obtain health insurance or a wise use of federal resources to spend so much on subsidizing coverage. What’s more puzzling, and more disturbing, is the still-raging division over the real-world effect of the ACA."

She says President Obama "over-promised when he told people that, if they liked their health insurance, they could keep it; by its own terms, the law set new standards for required coverage. Certainly, some individuals, particularly younger and healthier customers, find themselves paying more; again, such winners and losers were an inevitable consequence of the individual mandate and minimum-coverage rules. Meantime, the scariest warnings — of employers rushing to drop coverage and insurance markets ensnared in death spirals of ever-rising premiums — have not come to pass.
Where the law has yet to fully deliver on its promises — and some wonder whether it will — is in the area of cost containment and quality improvement."

Marcus backs up her assessment with facts. For example, "Health-care costs and premiums for employer-sponsored insurance (the way most of us obtain coverage) have been rising at their lowest levels in years. On the exchanges, premium increases during the law’s second year mirrored that modest growth — averaging 2 percent on some mid-range plans and 4 percent on the lowest-cost ones, according to the Kaiser Family Foundation."

Friday, March 27, 2015

How has the federal health-reform law changed your care?

Despite the controversy that continues to surround the Patient Protection and Affordable Act five years after its passage, it has probably changed the way your health care is delivered as it drives new models of payment, forces providers to approach care differently, and changes how health care is evaluated, Kavita Patel and Domitilla Masi report for the Brookings Institution.

Here are five ways the authors say that your health care might be different than it was five years ago because of the reform law:

Your physician might be part of a patient care team. New payment models in the ACA encourage an interdisciplinary team-based approach, which evidence shows "can lead to higher quality care and better health outcomes for patient." This approach allows the physician to spend more time diagnosing and devising a treatment plan, while the patient may spend more time interacting with non-physician staff for support care.

Prevention and wellness are more important than ever. The ACA requires health plans to cover all preventive screenings, immunizations and well visits for women at no cost, as part of the minimum benefits required in order for health-insurance plans to participate in exchanges like Kynect. The new payment models also pay physicians who work toward keeping their patients healthy, instead of just treating them when they are sick. " Since the policy took effect in September 2010 it is estimated that an additional 76 million people now receive preventive care," the authors write.

You may have better access to care on evenings and weekends. New payment models are driving this change as practices are often required to offer extended hours to decrease the overuse of emergency departments. Many offices now offer clinical advice around the clock with a clinician who has immediate access to their medical records.

Chances are your health information is being stored in an electronic health record, not a paper file. A separate law encouraged the use of EHRs, but "participation in the new ACA-promoted delivery models is practically impossible" without them. And while EHRs can be used to greatly improve patient care, not all EHRs are created equal and it will take time before patients see seamless integration and exchange between different doctors and settings in "real-time".

You can access care remotely, wherever you are. Doctors are using mobile technology and tele-health in rural and remote areas to provide more efficient care to patients. Insurance companies and employers are beginning to recognize this mode of treatment not only as a way to save money, but to also provide timely access to care, that does not involve the emergency room.

Tuesday, March 24, 2015

Health reform law has been good for hospital finances, health-care costs, Obama administration says

U.S. hospitals have saved billions of dollars because the federal health-reform law has provided coverage for patients who were once charity cases, the Obama administration announced Monday, the fifth anniversary of the Patient Protection and Affordable Care Act.

"Hospitals also saw fewer emergency room visits, which rack up far higher costs and often leave hospitals with the tab," Sarah Ferris writes for The Hill, which covers Congress. "The government’s report, which focuses on the benefits of Medicaid expansion, is an effort to entice states that have been politically resistant to expanding the program."

Kentucky hospitals have acknowledged that the law has reduced their losses from "uncompensated care," but say other aspects of the law have created a mixed effect, depending partly on hospitals' ability to adapt. The increase in coverage has brought hospitals much more money, but they say continued problems with managed-care Medicaid have cause them financial difficulty.

From paying patients' point of view, the law appears to have reduced inflation in health-care costs, but has not achieved advocates' goal of reducing costs. A White House report said, "Since the Affordable Care Act was enacted, health care prices have risen at the slowest rate in nearly 50 years. Thanks to exceptionally slow growth in per-person costs throughout our health care system, national health expenditures grew at the slowest rate on record from 2010 through 2013."

For the White House's Kentucky-specific list of benefits of the law, click here.

Reform law 'quietly accomplishing the goals it was created to achieve,' McClatchy Newspapers reporter writes

The federal health-reform law is still controversial and still facing a legal challenge, but "is quietly accomplishing the goals it was created to achieve," Washington correspondent Tony Pugh reported for McClatchy Newspapers on the occasion of the law's fifth anniversary. (The Lexington Herald-Leader is a McClatchy paper.)

"The nation’s uninsured rate has plummeted as more Americans enroll in Medicaid or in federal and state marketplace coverage," Pugh notes. "The law’s consumer protections and insurance-benefit requirements have improved the quality of coverage for millions of people who get health insurance outside the workplace. Premiums for marketplace health insurance have largely been reasonable and have increased only moderately thus far. Long-term cost estimates for providing coverage under the law have been falling."

Howver, Pugh writes, "The law may never overcome the bitter politics that surrounded its enactment and that partly define its legacy. Long viewed as a government overreach, the health-care law has been problematic for those who want the private insurance market to dictate who gets health insurance and what it should cost. . . . Moreover, the law’s requirement that most Americans have health insurance is seen as an infringement on individual freedom. The Supreme Court ruled in June 2012 that the so-called individual mandate didn’t violate the Constitution."

The White House issued a state-specific list of the law's benefits. For Kentucky's, click here.

Sunday, March 22, 2015

Obama says health-reform law working better than expected

President Obama made this statement on the fifth anniversary of the Patient Protection and Affordable Care Act:

On the five-year anniversary of the Affordable Care Act, one thing couldn’t be clearer:  This law is working, and in many ways, it’s working even better than anticipated.

After five years of the Affordable Care Act, more than 16 million uninsured Americans have gained the security of health insurance – an achievement that has cut the ranks of the uninsured by nearly one third.  These aren’t just numbers.  Because of this law, there are parents who can finally afford to take their kids to the doctor.  There are families who no longer risk losing their home or savings just because someone gets sick.  There are young people free to pursue their dreams and start their own business without worrying about losing access to healthcare.  There are Americans who, without this law, would not be alive today.

For Americans who already had insurance before this law was passed, the Affordable Care Act has meant new savings and new protections.  Today, tens of millions of Americans with pre-existing conditions are no longer at risk of being denied coverage.  Women no longer have to worry about being charged more just for being women.  Millions of young people have been able to stay on their parents’ plan until they turn 26.  More than 9 million seniors and people with disabilities have saved an average of $1,600 per person on their prescription medicine, over $15 billion in all since the Affordable Care Act became law.  More than 70 million Americans have gained access to preventive care, including contraceptive services, with no additional out-of-pocket costs.  And the law has helped improve the quality of health care: it’s a major reason we saw 50,000 fewer preventable patient deaths in hospitals over the last three years of data. 

The cynics said this law would kill jobs and cripple our economy.  Despite the fact that our businesses have created nearly 12 million new jobs since this law was passed, some still insist it’s a threat.  But a growing body of evidence – actual facts – shows that the Affordable Care Act is good for our economy.  In stark contrast to predictions that this law would cause premiums to skyrocket, last year the growth in health care premium costs for businesses matched its lowest level on record.  If premiums had kept growing over the last four years at the rate they had in the last decade, the average family premium would be $1,800 higher than it is today.  That’s $1,800 that stays in your pocket or doesn’t come out of your paycheck.  And in part because health care prices have grown at their slowest rate in nearly 50 years since this law was passed, we’ve been able to cut our deficits by two-thirds.  Health care costs that have long been the biggest factor driving our projected long-term up deficits up are now the single biggest factor driving those deficits down. 

The Affordable Care Act has been the subject of more scrutiny, more rumor, more attempts to dismantle and undermine it than just about any law in recent history.  But five years later, it is succeeding – in fact, it’s working better than even many of its supporters expected.  It’s time to embrace reality.  Instead of trying yet again to repeal the Affordable Care Act and allowing special interests to write their own rules, we should work together to keep improving our healthcare system for everybody.  Instead of kicking millions off their insurance and doubling the number of uninsured Americans, as the House Republican budget would do, we should work together to make sure every American has a chance to get covered.


Five years ago, we declared that in America, quality, affordable health care is not a privilege, it is a right.  And I’ll never stop working to protect that right for those who already have it, and extend it to those who don’t, so that all of us can experience the blessings of life, liberty, and the pursuit of happiness in this country we love.  

As tax deadline nears, most uninsured appear likely to choose penalty; some with coverage are having to refund part of subsidy

Kentucky Health News

Most people facing a tax penalty for not having health insurance appear likely to pay it instead of taking advantage of a special opportunity to but coverage and minimize the penalty.

"Major tax-preparation firms say many customers are paying the penalty and not getting health insurance," reports Stephanie Armour of The Wall Street Journal. "Research also suggests that many people who lack health insurance will pay the penalty and not get covered this year."

Many polls have found that many if not most people without health insurance are unaware that they are subject to a tax penalty under the federal health-reform law. That percentage appears to be declining as they prepare their income-tax returns, but a poll taken in late February found that when told of the penalty, only 12 percent of the uninsured said they would get coverage.

For many people, the choice is simply financial, since coverage for them would be more expensive than the penalty -- 1 percent of their income, or $95 per adult or $47.50 per child, whichever is larger. Others say they don't need coverage, and some object to the penalty or the law altogether.

The penalty will increase to 2 percent of income and $325 per adult or $167.50 per child for the 2015 tax year, so if you are uninsured and don't qualify for Medicaid or one of the law's exemptions, the end of the special enrollment period, April 30, is the last chance to avoid that penalty.

"In late February, H & R Block reported that its uninsured clients had paid an average penalty of $172," reports Abby Goodnough of The New York Times. "The money comes out of refunds, while people who do not get refunds are required to pay the Internal Revenue Service by April 15."

Some people who have coverage "might find another unpleasant surprise: As many as half the nearly 7 million Americans who got subsidies to offset their premiums may have to refund money to the government, according to an estimate by H & R Block," the Journal reports. "The subsidies are based on consumers’ own projections of their 2014 income, but some estimated incorrectly and received overly generous credits. Those people will see smaller-than-expected refunds or could owe the government money."

"H & R Block also found that as of Feb. 24, just over half of its clients with subsidized marketplace coverage had to repay a portion of their subsidy because their 2014 income turned out to be higher than what they estimated when they applied for coverage," the Times reports. "The process includes "new forms that even seasoned preparers are finding confusing."

The Obama administration announced last month that 800,000 people with insurance bought under the reform law had received incorrect information needed for their tax returns. About 10 percent of them have still not received corrected forms, it announced Friday. "The administration said people who have not received the corrected forms do not have to wait to file their taxes and will not have to pay any additional tax due to the effort," The Hill reports.

The Wall Street Journal reports, "Consumers who already filed their tax returns using the incorrect forms provided though state or federal exchanges won’t be required to file amended forms, and the Internal Revenue Service won’t assess additional taxes, said Mark Mazur, the Treasury Department’s assistant secretary for tax policy."

Thursday, March 19, 2015

Community health groups, with focus on prevention, fight to be part of new setup for lowering health costs, improving outcomes

The Patient Protection and Affordable Care Act is forcing doctors and hospitals to collaborate on lowering health-care costs while improving health outcomes. Community health groups that focus on preventive care are battling to be included as part of the solution, Laura Ungar reports for The Courier-Journal and USA Today.

One way physicians and hospitals are coming together to "reduce the duplication of services and keep large groups of patients well" is by forming accountable care organizations. Community health groups are having to fight for a "seat at the table" in these "doctor-dominated boards of ACOs," Ungar writes.

Such groups often offer less expensive, non-medical solutions for preventive health, according to a 2014 report by a North Carolina physicians' coalition. Some ACOs are beginning to include them as partners, but Bo Bobbitt, a Raleigh health-care lawyer who was lead author of the report, told Ungar, "The bad news is that the gap between the medical system treating illness and disease and the community health system was larger than we had feared."

Jose Pagan, a health economist who directs the New York Academy of Medicine's Center for Health Innovation, told Ungar that another key challenge is that doctors and hospitals are going to keep working to keep the money flowing their way. "If you go to a surgeon for a solution, they're not going to give you massage therapy," he says. "There's going to be progress, but it's going to be very slow."

Traditionally U.S. health care has focused its attention on "costly medical intervention," Ungar reports, instead of lifestyle changes, with only 3 percent of the $2.6 trillion health-care budget being spent public health and prevention, despite preventable chronic conditions accounting for 75 percent of medical care, according to a 2012 Institute of Medicine report.

"Compared to even the best medical therapy, we can decrease heart attacks, strokes and deaths by between 35 percent and 45 percent by changing lifestyle," Paul Rogers, a Louisville cardiologist at one of KentuckyOne Health System's healthy lifestyle centers, told Ungar.

For example, losing about 10 percent of weight reduces cardiac risks significantly, and losing 15 to 20 percent begins to reverse diabetes, lowers blood pressure, improves sleep and improves cholesterol level, Rogers said.

Another challenge for community-based programs is that little money goes into research on wellness programs, "and without studies, few will invest in their programs," Ungar notes.

Some members of Congress don't see nutrition, physical fitness or stop-smoking campaigns as health funding and gripe about the "nanny factor," Georges Benjamin, a physician who is executive director of the American Public Health Association, told Ungar.

As a result, "annual funding authorized by the ACA for the Prevention and Public Health Fund was supposed to hit $2 billion starting in 2015 but won't reach that level until at least 2022," Ungar reports.

Lifestyle changes are known to help chronic conditions, and Ungar gives many examples in the article. Here is one: Kevin French, 57, a construction contractor in Louisville, told Ungar that he began having chest pain and had to have two stents implanted in his heart in 1993.  And through cardiac rehab, he learned that his previous eating habits, which included lots of fast food, lack of exercise and smoking, played a big part in his heart problems. But with the help of the healthy lifestyle center, he said he  has "basically changed everything" about  his lifestyle and that's "improved not only his health but his family's as well."