Showing posts with label physicians. Show all posts

Sunday, June 21, 2015

Kentucky is cracking down on Suboxone, a heroin substitute that has become a big part of the illegal trade in painkillers

A drug that was supposed to help people get off heroin has "created a new cash-for-pills market and a street trade" that state officials are trying to stop, Mary Meehan reports for the Lexington Herald-Leader.

The drug is buprenorphine, the active ingredient in the brand-name drugs Suboxone and Subutex, which became more popular in 2012, when the state cracked down on "pill mills" that were freely handing out prescriptions for painkillers. "A lot of the pill mills morphed into facilities that dispense these prescriptions," Dr. John Langefeld, medical director for the state's Medicaid program, told Meehan.

Also, Meehan writes, the Patient Protection and Affordable Care Act required insurance plans to cover treatment for substance abuse, and "as more Medicaid patients and others got health-insurance coverage, more people obtained prescriptions for buprenorphine, Langefeld said. . . . According to a state report, one user obtained prescriptions from nine doctors."
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

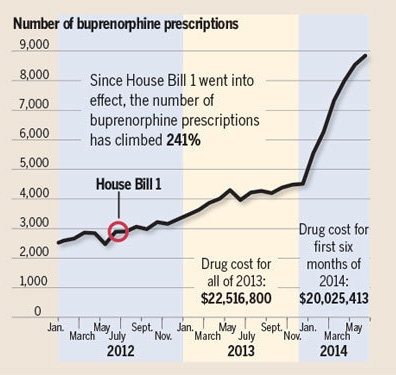
Lexington Herald-Leader chart by Chris Ware from state data
Use of the drug in Kentucky "has increased 241 percent since 2012," Meehan reports. "And 80 percent of the prescriptions for it were being written by 20 percent of the state's 470 certified prescribers, said Dr. Allen Brenzel, medical director of the state's Department of Behavioral Health. . . . Since 2011, 10 doctors have been sanctioned by the Kentucky Board of Medical Licensure because of problems prescribing Suboxone."

Suboxone is supposed to be taken in conjunction with therapy and drug testing. "a patient receives a controlled dose of a legal drug as the dose is tapered by a physician for a safe and effective withdrawal," Meehan notes. However, "doctors started to see Suboxone patients on a cash basis, asking for as much as $300 for an office visit that included a prescription for the maximum allowable amount of Suboxone. Patients often received no therapy or drug testing. Some patients were on the maximum dose indefinitely, Brenzel said." Some doctors prescribed the drug with other painkillers, creating an illegal market.

To prevent such abuse by unscrupulous doctors, the medical-licensure board has issued regulations that require "more physician education and the requirement that the drug be prescribed only for medically supervised withdrawal and not be given to pregnant women," Meehan writes. "Patients should also be closely monitored and drug tested. If those rules are not followed, a doctor can face sanctions or restrictions to his medical license."

Suboxone was in the national news recently because the accused killer in the Charleston, S.C., shootings was arrested for illegal possession of it four months ago at a South Carolina shopping mall, the Herald-Leader notes.
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Saturday, June 20, 2015

Three doctors, nine others in western half of Kentucky are indicted in the largest-ever federal 'takedown' of Medicaid fraud

Former Dr. Fred Gott of Bowling Green was arrested.
(Photo: Miranda Pederson, Bowling Green Daily News)
Twelve people in the western half of Kentucky, including three doctors, have been charged with Medicaid fraud in what the federal government calls its biggest-ever "takedown" of the problem, Andrew Wolfson of The Courier-Journal reports.

The indictments allege "a half-dozen schemes involving nearly $8 million in alleged fraudulent billings," Wolfson writes. "The offenses include $5 million in false billings for muscle-relaxant injections that were never delivered to patients, as well as a staged car wreck in which three people allegedly conspired to get controlled substances and fraudulent reimbursements."

In another case, Wolfson reports, "a medical practice that treated car wreck patients is accused of using the DEA numbers of nurse practitioners to order hydrocodone for herself and falsely billing it to an insurance company. Nationally, the sweep resulted in charges against 243 people, including 46 doctors, nurses and other licensed medical professionals."

John Kuhn, acting U.S. attorney for the Western District of Kentucky, told Wolfson that about $1 billion of annual Medicare and Medicaid expenses are fraudulent. Medicare is the federal health-insurance program for people over 65; Medicaid is the federal-state program for the poor and disabled.

Former Dr. Fred Gott of Bowling Green, a 63-year-old cardiologist, was charged with "conspiracy to dispense controlled substances, health care fraud and money laundering," Deborah Highland reports for the Bowling Green Daily News. "The Bowling Green-Warren County Drug Task Force opened an investigation into Gott’s practices after Warren County Coroner Kevin Kirby alerted the task force about drug overdose deaths involving Gott’s patients, task force director Tommy Loving said."

Saturday, June 13, 2015

Seniors get a lot of anti-anxiety drugs, sometimes in dangerous combination with narcotics; Ky. ranks third in the nation in that

When Medicare's drug program, called Part D, was put into place more than a decade ago, Congress decided to not pay for anti-anxiety medications. In 2013, when Medicare started paying for them, the program went from spending nothing for these medications to paying more than $377 million, Charles Ornstein and Ryann Grochowski Jones report for ProPublica, a nonprofit, investigative news organization.

Using anti-anxiety drugs in combination with narcotics increases the risk of overdoses, but Kentucky has many doctors who prescribe a lot of both. More than 100 Kentucky doctors each wrote at least 1,000 prescriptions for both types of drugs in 2013, according to data compiled by ProPublica.

That ranked Kentucky third in the nation, trailing only Florida and Alabama. Other southeastern states dominated the top 10. California, the nation's most populous state, ranked eighth; Tennessee was fourth and Ohio was ninth.

ProPublica has an application that lets you look up, by doctors' names, cities or ZIP codes, the number of Medicare claims they filed in 2013, the amount of money, the number of patients and the number of prescriptions for brand-name drugs.

The anti-anxiety drugs, some known as benzodiazepines, include popular tranquilizers such as Valium, Xanax and Ativan. 

Lawmakers initially chose to keep them out of Medicare Part D because they had been linked to abuse and an increased risk of falls among the elderly. Doctors kept prescribing them to Medicare enrollees, who found other ways to pay for them.

In 2013, the year Medicare started covering benzodiazepines, it paid for nearly 40 million prescriptions, ProPublica found. Generic versions of Xanax (alprazolam), Ativan (lorazepam) and Klonopin (clonazepam) were among the top 32 most-prescribed medications in Medicare Part D that year.

The American Geriatrics Society "discourages the use of benzodiazepines in seniors for agitation, insomnia or delirium because they can be habit-forming and disorienting and their effects last longer in older patients." The society does say the drugs "are appropriate to treat seizure disorders, severe anxiety, withdrawal and in end-of-life care," ProPublica notes.

One geriatric psychiatrist told ProPublica that the drugs are a "very real safety concern" for the elderly, and that he and others in his field don't use them as a "first-, second-, or third- line of treatment." Some geriatric psychiatrists have voiced concerns that these drugs are now being used instead of antipsychotics, since Medicare has pushed to reduce the use of antipsychotics, particularly in nursing homes, because of their risks.

Several doctors who rank among Medicare's top prescribers of the drugs told ProPublica that any risks of anti-anxiety drugs are outweighed by their benefits. One said that the drugs worked well for his patients, many of whom were trying to kick addictions to narcotics, but struggled with anxiety and depression.

However, ProPublica also found that some doctors appear to be prescribing benzodiazepines and narcotic painkillers to the same patients, which increased the risk of misuse and overdose. That's where Kentucky ranked third.

Dr. Leonard J. Paulozzi, a medical epidemiologist at the federal Centers for Disease Control and Prevention, co-authored an analysis showing that benzodiazepines were involved in about 30 percent of the fatal narcotic overdoses that occurred nationwide in 2010, ProPublica reports.

Wednesday, June 10, 2015

Dr. Steven J. Stack of Lexington is sworn in as 170th president of the American Medical Association

Dr. Steven J. Stack, an emergency physician practicing in Lexington, was sworn in as the 170th president of the American Medical Association, the nation’s largest physician organization.

Dr. Steven J. Stack
He is the organization’s youngest president in the past 160 years and is the first board-certified emergency-room physician elected to the post.

Stack says he will focus his tenure on advancing the AMA’s three strategic areas: improving health outcomes for those with pre-diabetes and hypertension; accelerating change in medical education to ensure physicians are prepared to meet the needs of a 21st century health care system; and enhancing physician satisfaction and practice sustainability.

"I am honored and privileged to be named president of an organization that is dedicated to the art and science of medicine and the betterment of public health and a profession that is working to improve the health of our nation," Stack said in a press release. "I look forward to serving on behalf of America’s physicians to not only create a brighter future for the medical profession but a healthier America one patient at time, one family at a time and one community at a time."

Stack gained national recognition for his expertise in health information technology while serving as chair of the AMA's Health Information Technology Advisory Group from 2007 to 2013. He has also served on multiple federal advisory groups for the Office of the National Coordinator for Health Information Technology and as Secretary for eHealth Initiative, a non-profit multi-stakeholder organization committed to advancing health care through health information technology.

In Kentucky, Stack has served as medical director of the emergency departments at Saint Joseph East in Lexington and Saint Joseph Mount Sterling, both part of KentuckyOne Health. He was also previous medical director of the emergency department at Baptist Memorial Hospital in Memphis, Tenn.

Stack was elected to the AMA Board of Trustees in 2006. In the last eight years, he has served in many leadership positions, including chair and secretary. Prior to his service on the AMA board, he was an elected leader in numerous state, national and specialty medical associations.

He is the second Lexington physician to lead the AMA in three years. Dr. Ardis Dee Hoven, an infectious-disease specialist at the University of Kentucky, led the group in 2013-14.

Sunday, May 31, 2015

Paducah Sun looks at two local doctors who write many prescriptions for painkillers; such local data are easily available

The Paducah Sun has used some easily available information about two local doctors to shine a local light on their heavy prescribing of opioids.

The story by Laurel Black begins, "As narcotic painkiller abuse has drawn more public attention, two Paducah physicians – who have been ranked high among prescribers of such drugs – have found themselves defending their practices."

The story cites The Courier-Journal's analysis of 2012 Medicare data that showed Dr. Yogesh Malla of Paducah was "the No. 3 prescriber of narcotic painkillers in the commonwealth. A USA Today article listed Dr. Riley Love, also of Paducah, as 20th in the nation. Both reports used information the news organization ProPublica obtained under the Freedom of Information Act."

The Sun offers a quick retort from the medical director of the pain-management center where Malla practices, paraphrasung him as saying "the reports omit or minimize important factors, such as the specialty of the physicians and the morphine equivalence of the drugs they prescribe."


Dr. Laxmaiah Manchikanti also said in his written statement that his group emphasizes drugs with lower abuse potential and that more than 92 percent of patients at such centers "are already on long-term opioids; consequently, the best we can do (at these centers) is reduce the dosage."

Manchikani is CEO of the American Society of Interventional Pain Physicians, a lobbying group that advocates monitoring of painlkiller prescriptions, and a leading contributor to a wde range of political causes. The Sun doesn't note the latter point, but focuses on the issues of painkiller abuse, a major problem in Kentucky.

"With more than 1,000 deaths per year, Kentucky in 2013 had the third-highest drug overdose mortality rate in the United States, according to the Trust for America's Health," Black notes.


As for the other doctor, the Sun reports, "ProPublica's data on Love, who practices at the Lourdes Pain Management Center, reports that 59 percent of his 1,141 patients filled one or more prescriptions for a Schedule 2 drug and 51 percent filled for a Schedule 3 drug. Both figures are above the average of 45 percent and 41 percent, respectively, for his specialty in Kentucky.


"A spokeswoman for Love said Lourdes center represents the only location in the region where Medicaid patients receive inpatient pain consultations," the Sun reports, quoting her: "The patients we see are often very sick, and the treatments and medications we provide are the last resort comfort measures so the patients can spend quality time with family" as they near death.

The story is behind the Sun's paywall.

Thursday, May 7, 2015

UK HealthCare offers help to primary-care clinics; university's top health official calls it 'a game changer' for rural health providers

The Kentucky Primary Care Association and the University of Kentucky have announced a new partnership to provide support services to primary care providers throughout Kentucky.

This "groundbreaking partnership" will provide KPCA, which includes more than 800 patient care providers, access to UK HealthCare's support services, such as supply chain contracts, medical professional placement services, practice transformation support and training, and an after-hours pediatric call triage center, according to press release.

The most notable feature of the partnership is that KPCA members will have access to UK's group purchasing contracts, giving them access to services at heavily discounted rates at no charge to the facilities. This is expected to create "significant" savings for more than 250 clinics throughout the state. UK's top health official called it "a game changer."

“Primary care physicians, especially those in rural areas, have the extra burden of high patient volume, limited staff, and stretched resources,” Dr. Michael Karpf, UK's executive vice president for health, said in the release. “By partnering, UK HealthCare and KPCA members can grow important programs and services for their patients while also controlling and reducing operating costs.”

KPCA Executive Director Joe Smith said, "By addressing some of these issues related to costs, clinics with already scarce resources can instead focus on improving the quality of care.We’ve had a longstanding association with the university and UK HealthCare, and this partnership elevates that relationship by adding a strong commitment to assisting rural doctors, nurses and practice managers, who face some of the toughest transitions taking place in medicine today.”

The partnership will also allow KPCA members access to staffing services that link candidates to vacancies across the state; to Patient Centered Medical Home consultants, who help practices transition to quality and value-based models of care; and to UK HealthCare's after-hours pediatric call triage service.

Thursday, April 16, 2015

Mount Sterling follows lead of another KentuckyOne Health hospital, in Bardstown, to host monthly 'Walk With a Doc'

Saint Joseph Mount Sterling is the second KentuckyOne Health hospital to host monthly "Walk With a Doc" events as part of a nationwide program that promotes walking as a great way to improve your health, while at the same time offering a place to get to know your local physicians in an informal setting as you walk together. The program also offers a complimentary health screenings at the event, says a news release from KentuckyOne Health.

Flaget Memorial Hospital in Bardstown, also part of KentuckyOne Health, began its "Walk With a Doc" program in March.

"According to America Walks, brisk walking has been shown to reduce body fat, lower blood pressure, increase high-density lipoprotein and even reduce risks of bone fracture. Not only that, it is also associated with lower mortality rates from cardiovascular disease and cancer," says the release.

The Mount Sterling walks begin at 9 a.m. on Saturday, April 25 at Easy Walker Park, located at 1395 Osborne Rd. For more information call 859-497-5556.

Friday, March 27, 2015

How has the federal health-reform law changed your care?

Despite the controversy that continues to surround the Patient Protection and Affordable Act five years after its passage, it has probably changed the way your health care is delivered as it drives new models of payment, forces providers to approach care differently, and changes how health care is evaluated, Kavita Patel and Domitilla Masi report for the Brookings Institution.

Here are five ways the authors say that your health care might be different than it was five years ago because of the reform law:

Your physician might be part of a patient care team. New payment models in the ACA encourage an interdisciplinary team-based approach, which evidence shows "can lead to higher quality care and better health outcomes for patient." This approach allows the physician to spend more time diagnosing and devising a treatment plan, while the patient may spend more time interacting with non-physician staff for support care.

Prevention and wellness are more important than ever. The ACA requires health plans to cover all preventive screenings, immunizations and well visits for women at no cost, as part of the minimum benefits required in order for health-insurance plans to participate in exchanges like Kynect. The new payment models also pay physicians who work toward keeping their patients healthy, instead of just treating them when they are sick. " Since the policy took effect in September 2010 it is estimated that an additional 76 million people now receive preventive care," the authors write.

You may have better access to care on evenings and weekends. New payment models are driving this change as practices are often required to offer extended hours to decrease the overuse of emergency departments. Many offices now offer clinical advice around the clock with a clinician who has immediate access to their medical records.

Chances are your health information is being stored in an electronic health record, not a paper file. A separate law encouraged the use of EHRs, but "participation in the new ACA-promoted delivery models is practically impossible" without them. And while EHRs can be used to greatly improve patient care, not all EHRs are created equal and it will take time before patients see seamless integration and exchange between different doctors and settings in "real-time".

You can access care remotely, wherever you are. Doctors are using mobile technology and tele-health in rural and remote areas to provide more efficient care to patients. Insurance companies and employers are beginning to recognize this mode of treatment not only as a way to save money, but to also provide timely access to care, that does not involve the emergency room.

Thursday, March 19, 2015

Community health groups, with focus on prevention, fight to be part of new setup for lowering health costs, improving outcomes

The Patient Protection and Affordable Care Act is forcing doctors and hospitals to collaborate on lowering health-care costs while improving health outcomes. Community health groups that focus on preventive care are battling to be included as part of the solution, Laura Ungar reports for The Courier-Journal and USA Today.

One way physicians and hospitals are coming together to "reduce the duplication of services and keep large groups of patients well" is by forming accountable care organizations. Community health groups are having to fight for a "seat at the table" in these "doctor-dominated boards of ACOs," Ungar writes.

Such groups often offer less expensive, non-medical solutions for preventive health, according to a 2014 report by a North Carolina physicians' coalition. Some ACOs are beginning to include them as partners, but Bo Bobbitt, a Raleigh health-care lawyer who was lead author of the report, told Ungar, "The bad news is that the gap between the medical system treating illness and disease and the community health system was larger than we had feared."

Jose Pagan, a health economist who directs the New York Academy of Medicine's Center for Health Innovation, told Ungar that another key challenge is that doctors and hospitals are going to keep working to keep the money flowing their way. "If you go to a surgeon for a solution, they're not going to give you massage therapy," he says. "There's going to be progress, but it's going to be very slow."

Traditionally U.S. health care has focused its attention on "costly medical intervention," Ungar reports, instead of lifestyle changes, with only 3 percent of the $2.6 trillion health-care budget being spent public health and prevention, despite preventable chronic conditions accounting for 75 percent of medical care, according to a 2012 Institute of Medicine report.

"Compared to even the best medical therapy, we can decrease heart attacks, strokes and deaths by between 35 percent and 45 percent by changing lifestyle," Paul Rogers, a Louisville cardiologist at one of KentuckyOne Health System's healthy lifestyle centers, told Ungar.

For example, losing about 10 percent of weight reduces cardiac risks significantly, and losing 15 to 20 percent begins to reverse diabetes, lowers blood pressure, improves sleep and improves cholesterol level, Rogers said.

Another challenge for community-based programs is that little money goes into research on wellness programs, "and without studies, few will invest in their programs," Ungar notes.

Some members of Congress don't see nutrition, physical fitness or stop-smoking campaigns as health funding and gripe about the "nanny factor," Georges Benjamin, a physician who is executive director of the American Public Health Association, told Ungar.

As a result, "annual funding authorized by the ACA for the Prevention and Public Health Fund was supposed to hit $2 billion starting in 2015 but won't reach that level until at least 2022," Ungar reports.

Lifestyle changes are known to help chronic conditions, and Ungar gives many examples in the article. Here is one: Kevin French, 57, a construction contractor in Louisville, told Ungar that he began having chest pain and had to have two stents implanted in his heart in 1993.  And through cardiac rehab, he learned that his previous eating habits, which included lots of fast food, lack of exercise and smoking, played a big part in his heart problems. But with the help of the healthy lifestyle center, he said he  has "basically changed everything" about  his lifestyle and that's "improved not only his health but his family's as well."

Wednesday, March 11, 2015

Advocates of state appeals for Medicaid managed-care claims make last-ditch effort to get it passed, by hijacking another bill

By Melissa Patrick
Kentucky Health News

FRANKFORT, Ky. -- Advocates of a bill to create a state appeals process for health-care providers to appeal decisions of Medicaid managed-care companies are trying to jam it through at the end this short legislative session on the coattails of an unrelated bill that appears to be uncontroversial.

Rep. Joni Jenkins
Senate Bill 120, sponsored by Sen. Ralph Alvarado, a Republican physician from Winchester, would create an administrative appeals process in the Cabinet for Health and Family Services, which opposes the idea. A Senate committee has attached Alvarado's language as an amendment to House Bill 71, sponsored by Rep. Joni Jenkins, D-Louisville, that would allow judges to order a person who is "incapacitated by alcohol and other drug abuse" into treatment.

"I think it has the potential of killing this bill," Jenkins said in an interview. "I heard there was a really large price tag put on [Senate Bill 120], a large fiscal load. So this late in a non-budget year, it is probably going to kill it."

Sen. Julie Raque Adams, chairperson of the Senate Health and Welfare Committee, disagreed. "Everybody in the Senate [is] very supportive of Rep. Jenkins' bill, and we have also passed out Senate Bill 120 from this chamber," she said in an interview.

SB 120 passed the Senate 35-0 on March 2. HB 71 passed the House 90-1 on Feb. 26.

Rep. Robert Benvenuti of Lexington, Republican co-chair of the Democrat-controlled House Health and Welfare Committee, said he thought SB 120 "has a lot of support" on the House floor if leaders of the House's Democratic majority allowed it to come up for a vote.

But to get a floor vote it must first come out of the committee, and that appears unlikely. The legislature can still pass bills on March 23 and March 24, after the 10-day recess for Democratic Gov. Steve Beshear to veto bills, but if he vetoes bills passed then there is no opportunity to override vetoes.

"I think it is a bill that properly sets up a process for providers who believe they have not been properly reimbursed to have some redress," Benvenuti said in an interview. "Our health care providers who serve this commonwealth need to have an avenue of redress so that they can be properly paid for medically necessary services that they provide."

Alvarado has said an administrative appeals process is necessary because managed-care organizations are denying claims for medically necessary treatments and then denying the providers' appeals, which means providers are not getting paid for their work.

The cabinet says it should not be responsible for an appeals process for MCOs because they do not have any legal authority between a contract made between a provider and the MCO. They have also said it would cost the state money. MCOs are paid a flat fee for each person whose care they manage, but an increase in approval of initially denied claims could give them leverage in negoiations for the next annual contract.

The fiscal note for this bill says the cabinet estimates its administrative cost for an appeals process would be at least $1 million a year, which would increase in later years. Alvarado maintains that the added cost to the state should be minimal.

Jenkins, whose nephew, Wesley, died of a heroin overdose two years ago, said that this is the fourth year she has tried to pass this bill, with a lack of funding to pay for the program its main obstacle, "but with the passage of the ACA, it has opened up private insurers and Medicaid to pay."

Jenkins said if the House didn't concur with the changes made by the Senate, she hoped the Senate would withdraw its amendment.

Adams said if the House didn't concur, she would be "very receptive" to going into conference committee to resolve their differences because Rep. Jenkins "has got a very important bill that we need to pass."

Monday, March 9, 2015

Bardstown hospital sponsors monthly 'Walk With a Doc'

Here's an interesting idea to promote physical activity and maybe even health literacy: take a walk with your doctor.

Flaget Memorial Hospital in Bardstown hosts monthly "Walk With a Doc" events as part of a nationwide program. Participants can also receive complementary health screenings at the event, says a news release from KentuckyOne Health, which owns Flaget.

"According to America Walks, brisk walking has been shown to reduce body fat, lower blood pressure, increase high-density lipoprotein, and even reduce risks of bone fracture," the release says. "Not only that, it is also associated with lower mortality rates from cardiovascular disease and cancer."

The walks begin at 10 a.m. on the second Saturday of each month, so the next one is March 14. The walks begin at the Court Square in the middle of Bardstown. For more information, call 502-350-5040.

Thursday, February 5, 2015

Senate OKs bill for review panels in medical lawsuits after lively debate between doctors, lawyers, others

This story, which was published Thursday morning, has been updated with action in the full Senate.
By Melissa Patrick
Kentucky Health News

FRANKFORT, Ky. -- The Senate has approved a bill that advocates say will help weed out "frivolous" medical malpractice lawsuits and speed up litigation for legitimate suits.

Alvarado
"Right now, Kentucky has one of the nations most litigation-friendly environments, making our commonwealth a prime and profitable target for personal injury lawyers preying upon our health care providers," Sen. Ralph Alvarado, R-Winchester, a physician and sponsor of Senate Bill 6, told the Senate Health and Welfare Committee. Opponents disputed that claim.

The Senate passed the bill Thursday 24-12. It is not expected to pass the House.

The bill would establish panels of three medical experts, two chosen by each side and the third chosen by the other two, to review suits against health-care providers to determine if the case has merit before the lawsuit can proceed. Panel findings would be admissible in court but not legally binding.

The Republican-controlled Senate passed a very similar bill last year but it got nowhere in the Democrat-controlled House, and its prospects are similar this time. However, Wednesday's committee meeting provided a detailed and lively explication of the issue, lasing almost two hours.

Vanessa Cantley, a Louisville personal injury attorney, told the committee that most medical malpractice cases are legitimate. She cited a Harvard University study published in the New England Journal of Medicine that concluded "portraits of a malpractice system that is stricken with frivolous litigation are overblown" and reported that 97 percent of claims for medical injury evaluated over a decade were deemed to be meritorious.

However, Michael Sutton of Louisville, a civil defense attorney, said defendants win 80 per cent of medical malpractice suits.

Cantley said there are 2,700 deaths in Kentucky each year due to purely preventable medical error, but, according to the state Department of Insurance, fewer than 500 lawsuits a year are filed by abuse and neglect victims. She spoke for the Kentucky Justice Association, formerly the Kentucky Academy of Trial Attorneys.

Alvarado and other opponents argued that Kentucky has become a haven for such lawsuits and bills like his have helped deter them. "Medical review panels are a proven solution for limiting baseless claims brought by a personal injury lawyer to ensure a faster, more efficient path for patients with legitimate claims, " he said.

Alvarado said the state is 4,000 doctors short of its need and the legal climate in Kentucky makes it hard to recruit and retain doctors. Sen. Julie Raque Adams, R-Louisville, the committee chair, said the expansion of Medicaid in Kentucky makes it all the more important to make the state attractive to doctors. "Anytime there's a paradigm shift, there are other policies that  need to go along with that paradigm shift," she said.

Dave Adkisson, president and CEO of the Kentucky Chamber of Commerce, said review panels "will stabilize our medical malpractice system and make our state more attractive" and "protect the legitimate cases while weeding out the meritless claims," which increase costs to consumers and employers through higher premiums and defensive medicine in the form of extra medical tests.


Kentucky's constitution bans laws that would cap damages
in lawsuits. (Care First Kentucky graphic)
Every state surrounding Kentucky offers some level of protection against medical malpractice, while Kentucky offers no legal protections for healthcare providers, according to Care First Kentucky, a business coalition supporting the bill.

Sen. Reggie Thomas, D-Lexington, a lawyer, argued that Kentucky already has laws to punish attorneys for filing frivolous cases. Alvarado said the rule isn't used much because judges "allow a lot of latitude," and Sutton said it is reserved for "really egregious conduct."

Cantley argued, subtly, that courts are the refuge for patients who suffer from abuse, neglect and malpractice. She said the federal Centers for Medicare and Medicaid Services has ranked Kentucky No. 1 in nursing-home deficiencies, and argued that state boards that discipline doctors do a poor job.

The full Senate's debate on the bill was cut short because the committee adopted a substitute version, preventing Democratic Leader Ray Jones of Pikeville, a plaintiffs' lawyer, from offering any of his amendments, which had been drafted to the original bill. Under traditional procedures, a bill gets its required readings on days between the committee meeting and the floor vote, but in recent years Republicans have given important bills readings before committee action, allowing a vote on them the day after they pass a committee.

Thursday, December 18, 2014

Ky. ranks 8th in the number of high-prescribing Medicare physicians for powerful narcotic painkillers and stimulants

Kentucky ranks eighth in Medicare physicians who are considered "high prescribers" of Schedule 2 medications, drugs that have the highest potential for abuse like oxycodone, fentanyl, morphine and Ritalin, according to an analysis of Medicare data analyzed by ProPublica, Laura Ungar reports for The Courier-Journal. About 1,000 Kentuckians die each year from drug overdoses.

Medicare's drug program, Part D, covers about 38 million seniors and disabled and pays for more than one of every four prescriptions dispensed in this country, Charles Ornstein and Ryann Grochowski Jones report for ProPublica, a non-profit investigative news organization.

Further analysis by The Courier-Journal found that Kentucky doctors prescribed narcotic painkillers to a "much larger percentage of their elderly and disabled patients" compared to other states, and that Kentucky had 11 of the 269 prescribers who wrote more than 3,000 prescriptions for Schedule II drugs under the program, Ungar reports.

"One in five doctors who wrote at least 3,000 prescriptions for Schedule 2 drugs have faced some kind of sanction or investigation, according to the ProPublica analysis," Ornstein and Jones write.

Kentucky's top prescribers, those with the largest numbers of Medicare patients who received at least one prescription for a narcotic painkiller in 2012, include three pain doctors, an adult-medicine physician and an internal-medicine doctor, Ungar reports.

In 2012, 12 of Medicare's top 20 prescribers of Schedule 2 drugs faced disciplinary actions by their state medical boards, Ornstein and Jones report. In Kentucky, only one of its top prescribers, Dr. Gregory Mick, a Lexington adult-medicine physician, has been disciplined by the Kentucky Board of Medical Licensure, which ordered him to stop prescribing controlled substances, Ungar reports.

The other four top prescribers told Ungar that "they are practicing good medicine and have legitimate reasons for having more than 1,000 Medicare patients each who received at least one narcotic painkiller prescription."

Beginning in mid-2015, Medicare will have the authority to kick doctors out of the program if they prescribe in abusive ways, Ornstein and Jones report. Medicare sent letters to 760 high prescribers in September "in hopes that they will examine their prescribing and make changes."

ProPublica obtained the data under the Freedom of Information Act to update its online Prescriber Checkup tool with the most recent numbers available and shared it with The Courier-Journal and other Gannett Co. news organizations. A Courier-Journal reporter further analyzed the information about Kentucky doctors.

Sunday, November 23, 2014

Conference focuses attention on importance of patient- and family-centered care, health education, communication

Health education, communicating with physicians, and patient- and family-centered care that empowers patients to be their own best health advocates, were some of the topics discussed at the Health Watch USA conference in Lexington this month.

Joycelyn Elders
“Patient empowerment is the right of the patient to take an active role in decisions about his or her own care,” said former U.S. surgeon general Joycelyn Elders, professor emeritus of pediatric endocrinology at the University of Arkansas. “But you can't make a good decision if you have not been educated. You can't keep an ignorant population healthy.”

Waiting until a person is old and set in their ways and then trying to teach them better health strategies doesn't work, Elders said. For patients to really be involved in their health, health education must start early.

“We must push for comprehensive health education in our school systems from kindergarten through 12th grade,” she said. “It is just as important as teaching reading, writing, and arithmetic. . . . We need to have science-based answers rather than ubiquitous myths. We need to protect people by arming them with correct information.”

Elders offered some practical suggestions to help patients become more empowered during their doctor's visits:
  • Take a trusted person with you.
  • Ask questions if you don't understand.
  • Bring all of your medications with you.
  • Write down questions and concerns before you go.
  • Ask your doctor to write down information and instructions discussed.
  • Make sure to tell your doctor if you have vision or hearing problems.

Elders said health education for physicians could also be improved, by putting more emphasis on preventive care and the treatment of chronic diseases, which are 75 percent of diseases in the United States, rather than acute diseases.

“We spend only 3 percent of our health-care dollars on keeping people well,” Elders said. “We have to do a better job. We haven’t educated our doctors.”

Karen D. Meyers
Karen D. Meyers, a lawyer who works with catastrophic-injury victims and health-care providers, said medical schools must start teaching doctors how to become better collaborators, not only between specialties, but with their patients as we move toward a model of patient and family centered care.

“They must learn to treat patients with dignity and respect, listen and share information with their patients, and allow patients to participate in their care,” said Meyers, who became an advocate for patient- and family-centered care after becoming a health advocate for her mother, who was in a coma for 40 days.

Elders said patient empowerment requires the patient to take some responsibility for his or her care, which requires respectful communication and shared decision-making between the doctor and the patient. The current physician-patient model of care does not support this concept, Elders said: “This has to change.”

Meyers concurred, saying physicians, hospitals and patients must change the attitude of “my patient, my treatment plan, my procedure, my case” to a model that recognizes that “everything about a patient's health belongs to the patient and their family.” She added, “Patients have to understand, because they are responsible for their care.”

Health Watch USA, based in Somerset, was founded by Dr. Kevin Kavanagh to promote health care transparency and patient advocacy, according to its website. For its report on the conference, in PDF format, click here.

Sunday, August 31, 2014

As nurse practitioners enjoy their new, state-granted authority, The Paducah Sun looks at the issue in far Western Kentucky

Kentucky law has expanded the rights of nurse practitioners, Laurel Black notes for The Paducah Sun: "Local practitioners say the move will provide patients with better access to care, but not everyone in the medical community embraces the idea."

The new law "gives nurse practitioners who have worked with a physician for four years the right to prescribe routine medications, such as those used to treat diabetes and blood pressure, without a doctor's involvement," Black writes. But nurse practitioners want it to go farther.

The American Association of Nurse Practitioners says "19 states and the District of Columbia allow nurse practitioners full autonomy. This means they're allowed to evaluate patients, order and interpret diagnostic tests, and initiate and manage treatments, including prescribing medications," Black reports. "As the population in the United States grows and ages, providers worry over a physician shortage -- as many as 130,600 by 2025, according to the Association of American Medical Colleges -- and some providers believe nurse practitioners could fill that gap if granted more independence."

"We want to be as independent as we can, because that gives better access to patients," said Amy Fennel, a nurse practitioner at the Paducah Neurosurgical Center, told Black.

"But the idea has met with opposition from organizations such as the American Medical Association," Black notes. "The AMA argues in support of physician-led teams, stating that nurse practitioners lack the education and training to practice on their own."

Black writes, "Local practitioners say their roles are different from those of physicians, and that practicing independently is well within the scope of their training. Elizabeth Scheidler, a nurse practitioner with Mercy Primary Care in Lyon County, who was a nurse for 12 years, told Black that her training was more patient-focused.

"That makes them a good fit for the current health care climate, where primary care physicians are at a premium, particularly in rural areas," Black writes. "Kentucky's law addresses only prescription of non-scheduled medications; controlled substances still require a collaborating physician. And there's still a ways to go before nurse practitioners are able to practice with complete autonomy in the state. For the time being, Scheidler says, the new law 'is a good compromise'." The legislature wrestled with the issue for years before passing the compromise this year. (Read more; subscription required)

Monday, August 18, 2014

Doctors of osteopathy are an increasing answer to the doctor shortage, as more osteopathic medical schools open

Doctors of osteopathy could be part of the solution to Kentucky's well-documented primary care doctor shortage, Laurel Black reports for The Paducah Sun.

"The American Association of Medical Colleges predicts that a growing population of aging people, health insurance expansion, and a freeze on Medicare funding for residency training positions will lead to a physician shortage of more than 90,000 by 2020," Black reports.

Rural areas are expected to be most affected by the shortage of physicians, especially in the area of primary care, Black writes. Kentucky is already experiencing this problem. A presentation at the 2013 Kentucky Rural Medical Educators Conference said Kentucky had a 1,287:1 primary care physician-to-citizen ratio, 557 short of the national average.


Despite this "looming doctor shortage," little attention has been given to osteopathic medicine as a possible solution, Black writes. But enrollment in osteopathic medicine, "which puts a focus on primary care and works to place its doctors in under-served regions," is growing.

"There are a lot of osteopathic schools. It's definitely a growing field," Griffin Bicking, a doctor of osteopathy and a vascular surgeon at Baptist Health Paducah, told Black.

"Graduates in osteopathic medicine have increased by more than 250 percent between 1980 and 2005, according to a study by the medical colleges' association. In 1980, there were 14 schools with fewer than 5,000 students in America; there are now 30 schools with more than 30,000 students," Black reports. "It's estimated that today nearly 30 percent of all medical school graduates are estimated to be doctors of osteopathy," or D.O.s.

The University of Pikeville's Kentucky College of Osteopathic Medicine has graduated more than 800 physicians since its inception in 1997, with 60 percent of these graduates serving primarily in rural healthcare facilities in Eastern Kentucky and other regions of Appalachia, according to its website.

New or relatively new osteopathic medical schools near Kentucky are in Harrogate, Tenn.; Lewisburg, West Virginia; and Blacksburg, Va.  Other adjoining states with such schools include Ohio, Illinois, Indiana and Missouri.

Black reports that the stigma associated with D.O.s is fading as people seek a more holistic approach to their health. She also notes that the most notable difference between D.O.s and a doctor with traditional training is a required 300 to 500 hours of training in osteopathic manipulative treatment. This training, known as OMT, involves the movement of patient's bones and muscles to treat illness and injury and is part of the controversy surrounding D.O.s, Black reports.

However, more than half of D.O.s "used OMT on less than 5 percent of their patients," according to a study reported in Academic Medicine, the journal of the medical colleges' association, Black writes.

"Curriculum-wise, it's pretty much the same," Bradley Albertson, an internist and pediatrician at Mercy Primary Care in Benton, told Black of osteopathic medicine, which also requires four years of training followed by an internship and a residency. "The differences are more political and social."

Albertson opted for a non-osteopathic residency after attending a college of osteopathy for medical school, telling Black it "would add legitimacy to his practice."

And while osteopathic schools try to push primary care, D.O.s can go into any field a traditional doctor can, and it usually pays more to specialize, Black writes.

Albertson told Black that he is not sure that osteopathic schools will be the solution to the predicted patient-doctor gap and suggest it will take a "variety of solutions," including giving nurse practitioners more privileges.

Sunday, July 6, 2014

Drug developed to treat addiction is being abused, so much that clinics have been opened to sell it

"Suboxone, a popular and highly touted medicine designed to get people off opioids such as painkillers and heroin, is increasingly being abused, sold on the streets and inappropriately prescribed, according to doctors and drug control and law enforcement officials," Laura Ungar reports for The Courier-Journal. "The drug combines buprenorphine, an opioid, and naloxone, which counters the effects of an overdose. Prescriptions for Suboxone and its generic equivalent rose 63 percent in Kentucky between the first quarter of 2012 and the first quarter of this year, to 113,713 from 69,640."

One reason is the state's crackdown on pain clinics that were little more than pill mills. "In lieu of that, now people are opening Suboxone clinics. Many are cash-only," Leanne Diakov, general counsel for the Kentucky Board of Medical Licensure, told Ungar. "We have seen some doctors in trouble with licenses or finances opening these clinics." Ungar found that 14 percent, or 45, of the 330 Kentucky physicians authorized to prescribe buprenorphine "have a history of discipline by the medical board."

Attorney General Jack Conway told Ungar that suboxone abuse "is certainly on my radar, but I've kind of been careful to tread lightly. Some people desperately need Suboxone. I view it as a treatment of last resort . . . not a magic pill for addiction." Doctors told Ungar that some addicts self-medicate with Suboxone and use it to stave off withdrawal symptoms "when they have nowhere else to turn," she writes.