Showing posts with label state government. Show all posts

Sunday, June 21, 2015

Kentucky is cracking down on Suboxone, a heroin substitute that has become a big part of the illegal trade in painkillers

A drug that was supposed to help people get off heroin has "created a new cash-for-pills market and a street trade" that state officials are trying to stop, Mary Meehan reports for the Lexington Herald-Leader.

The drug is buprenorphine, the active ingredient in the brand-name drugs Suboxone and Subutex, which became more popular in 2012, when the state cracked down on "pill mills" that were freely handing out prescriptions for painkillers. "A lot of the pill mills morphed into facilities that dispense these prescriptions," Dr. John Langefeld, medical director for the state's Medicaid program, told Meehan.

Also, Meehan writes, the Patient Protection and Affordable Care Act required insurance plans to cover treatment for substance abuse, and "as more Medicaid patients and others got health-insurance coverage, more people obtained prescriptions for buprenorphine, Langefeld said. . . . According to a state report, one user obtained prescriptions from nine doctors."
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

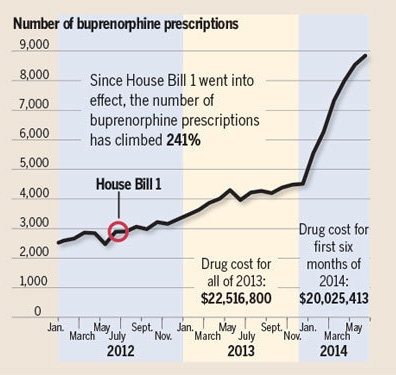
Lexington Herald-Leader chart by Chris Ware from state data
Use of the drug in Kentucky "has increased 241 percent since 2012," Meehan reports. "And 80 percent of the prescriptions for it were being written by 20 percent of the state's 470 certified prescribers, said Dr. Allen Brenzel, medical director of the state's Department of Behavioral Health. . . . Since 2011, 10 doctors have been sanctioned by the Kentucky Board of Medical Licensure because of problems prescribing Suboxone."

Suboxone is supposed to be taken in conjunction with therapy and drug testing. "a patient receives a controlled dose of a legal drug as the dose is tapered by a physician for a safe and effective withdrawal," Meehan notes. However, "doctors started to see Suboxone patients on a cash basis, asking for as much as $300 for an office visit that included a prescription for the maximum allowable amount of Suboxone. Patients often received no therapy or drug testing. Some patients were on the maximum dose indefinitely, Brenzel said." Some doctors prescribed the drug with other painkillers, creating an illegal market.

To prevent such abuse by unscrupulous doctors, the medical-licensure board has issued regulations that require "more physician education and the requirement that the drug be prescribed only for medically supervised withdrawal and not be given to pregnant women," Meehan writes. "Patients should also be closely monitored and drug tested. If those rules are not followed, a doctor can face sanctions or restrictions to his medical license."

Suboxone was in the national news recently because the accused killer in the Charleston, S.C., shootings was arrested for illegal possession of it four months ago at a South Carolina shopping mall, the Herald-Leader notes.
Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Read more here: http://www.kentucky.com/2015/06/20/3910362_the-drug-that-was-supposed-to.html?rh=1#storylink=cpy

Friday, June 19, 2015

Republican legislators question cabinet's figures on managed-care payments and cost projections for Medicaid expansion

Audrey Haynes (cn|2 image)
"When Audrey Haynes sat down before the legislature’s Medicaid Oversight and Advisory Committee Wednesday, she expected the data she brought would persuade lawmakers that Kentucky’s expansion of Medicaid has been good for the state," Ronnie Ellis reports for CNHI News Service. "The secretary of the Cabinet for Health and Family Services, which administers the Medicaid program also may have expected her statistics to ease unhappiness with the state’s move to managed care for most Medicaid services."

"It didn’t happen," Ellis writes. "At least she didn’t persuade Republican members who openly questioned the validity of the cabinet’s data, a couple stopping just short of saying the cabinet is making up the numbers" about payments to providers by managed-care organizations, which it says are 99 percent on time. “The numbers do not appear to represent the reality on the ground,” Rep. Richard Benvenuti, R-Lexington, said after the meeting.

Sen. Ralph Alvarado
“I think those are false,” Sen. Ralph Alvarado, R-Winchester, said after the meeting. “I don’t know if they’re lying, but somebody is providing bad information.”

During the meeting, Alvarado read "segments of letters from providers who have not received full reimbursements from managed care organizations," reports Kevin Wheatley of cable channel cn|2's "Pure Politics."

"Haynes referenced a report from CHFS which showed that over 90 percent of Medicaid claims are being paid in a timely manner," reports the blog of the Kentucky Chamber of Commerce. "Sen. Alvarado replied that this statistic does not match what he is hearing from his constituents and medical providers." Haynes addressed the managed-care issue in her PowerPoint presentation, downloadable here.

Rep. David Watkins, D-Henderson, a retired physician and co-chair of the committee, "urged the panel to find ways to improve managed care."

Watkins said the managed-care organizations, which are insurance companies or their subsidiaries, should come before the committee to answer questions. “I’m not totally satisfied that they’re doing quite as good a job as your report here would portray,” he told Haynes. “I think they need to be more accountable. I think they need to be more responsive to the providers who actually are doing work in the field.”

The MCOs will appear before the joint House-Senate committee Aug. 19, Brad Bowman reports for The State Journal in Frankfort. For cn|2's three-minute clip of the discussion between Haynes and Alvarado, via YouTube, click here.

The Republican lawmakers also voiced skepticism, but offered no contrary evidence, about the cost of expanding Medicaid to households with incomes up to 138 percent of the federal poverty level, from the previous limit of 69 percent. Under the Patient Protection and Affordable Care Act, the federal government is paying the entire cost of the expansion until next year, when the state will begin paying a small part, rising to the law's cap of 10 percent in 2020.

Haynes noted projections for Democratic Gov. Steve Beshear's administration that the expansion would add $30.1 billion to the state's economy through 2021, and would pay for itself until then, even after the state starts picking up part of the cost. The numbers were not new; they were part of a study by Deloitte Consulting and the University of Louisville that Beshear released in February.

Republicans focused on the prediction that the expansion would cost the state a net $45 million in 2021. "I know that seems like a way long ways off and some of you may no longer even be in the position to deal with it, but some of us probably will and the taxpayers will," said Alvarado, a physician.

Haynes "stated that she believed with the financial boost to the economy through jobs, the costs will be offset," the blog of the Kentucky Chamber of Commerce reports.

“Now that we’re seeing the lowest unemployment that we’ve seen in our state in quite a number of years, I’m sure each of you are amazed at how that we’ve had all 120 counties in our state where the unemployment rate has gone down,” Haynes said. “As this state continues to generate revenue and hopefully, as is planned, this is a bridge program for people who basically are hard-working people, but their employer does not provide insurance or they have children and therefore that qualifies them from an income basis for Medicaid.”


Thursday, June 11, 2015

New license plate would promote outdoor recreation, support environmental education programs; 900 buyers needed to start

A new "Let's Go Outside" license plate is being offered to give Kentucky motorists the opportunity to promote the health and environmental benefits of outdoor recreation.

First Lady Jane Beshear unveiled the license plate June 10. She said that encouraging children to play outside will help improve their health and noted that "Kentucky has one of the highest childhood obesity rates in the nation," reports to The Lane Report.

Proceeds from the specialty plate will support the work of the Kentucky Environmental Education Council, including coordinating the Kentucky Green and Healthy Schools program and certifying professional environmental educators.

“Kentuckians have said in surveys that children not spending enough time outside is a major concern,” KEEC Executive Director Elizabeth Schmitz said. “One of our goals is to encourage children to embrace the outdoors and to teach them the importance of a clean environment for our health and preservation."

The Kentucky Environmental Education Council needs 900 applications, each accompanied by a $25 donation, before any plates will be manufactured.

Submitting the application does not obligate you to purchase the plate, but your donation will be credited toward the purchase of a plate once they are in production. If not enough applications are received, your $25 will be considered a tax-deductible donation.

A link to download the application is available at www.keec.ky.gov/LetsGoOutside.

Sunday, May 24, 2015

State health commissioner backs needle exchanges, most controversial part of anti-heroin legislation passed this year

The Kentucky General Assembly cracked down in 2012 on "pill mills" that dispense painkillers irresponsibly, and addicts responded by going for heroin, creating a big problem in much of the state. The 2015 legislature passed laws to crack down on heroin, including local needle-exchange programs, the most controversial feature of the package.

In a column distributed to Kentucky newspapers, state Health Commissioner Stephanie Mayfield defends and promotes the local programs, which are subject to local approval.

“To some, a needle exchange may sound like a program that helps intravenous drug users feed their habit,” Mayfield writes. “To the contrary, the intent of an NEP is to protect public health and create a path for heroin users to get treatment while preventing the spread of diseases through the sharing of needles.

Needle exchanges reduce the number of HIV/AIDS and hepatitis cases in a community, Mayfield writes. "The use or even the accidental stick of a dirty needle can lead to hepatitis, HIV/AIDS infection and other dangerous diseases. . . . About 15 percent of all HIV cases that have occurred in Kentucky have been among injecting drug users."

Stephanie M. Gibson
Mayfield also says needle exchanges protecting people from accidental sticks from dirty needles discarded in public places. "Intravenous drug users submit dirty needles to the NEP for proper disposal in exchange for clean needles," she writes. "Researchers have also found that injecting drug users who participated in an exchange were more likely to reduce or stop injecting than drug users who had not participated in a needle exchange."

Research has also shown that needle exchanges "do not encourage the initiation of drug use nor do they increase the frequency of drug use among current users," Mayfield writes, noting that there are 203 such programs in 34 states.

"The presence of NEPs in communities does not expand drug-related networks nor does it increase crime rates. . . . Needle exchange programs actually create a path for injecting drug users to get help because the programs offer information on how to find available treatment options. In fact, NEP participants are more likely to enter a drug treatment program than nonparticipants."

More recent studies show that needle exchanges "provide opportunities for disease testing and education leading to a decline of at-risk behaviors, resulting in HIV incidence dropping as much as 80 percent within this population," Mayfield writes. "Many Kentucky communities are desperate for the ability to reach out to members who suffer from addiction, to help slow the spread of diseases and provide treatment referrals to people they might otherwise never have the chance to reach. This law gives them that opportunity."

Sunday, April 19, 2015

Kentucky re-bidding Medicaid managed care contracts to address complaints of patients, advocates and health-care providers

By Melissa Patrick
Kentucky Health News

State officials are re-bidding Medicaid managed-care contracts that cover more than 1.1 million Kentuckians. The news came as a delight and surprise to many health-care providers and patient advocates.

“I was both stunned and thrilled by the announcement. I did not know it was coming,” Sheila Schuster, a Louisville mental-health advocate, told Tom Loftus of The Courier-Journal. “A number of the changes that they say will be part of the new contracts are things those of us in the behavioral health community have brought up time and time again.”

Kentucky changed to Medicaid managed care from a traditional fee-for-service model in 2011 to fill a projected budget overrun of $166 million. Health Secretary Audrey Haynes said in a news release that doing so has "saved Kentucky taxpayers more than $1.3 billion in state and federal funds" and had also improved the delivery of health care to the Medicaid population.

"However, after several years of experience, we determined it was time to retool, rebid and strengthen the contracts to appropriately address concerns expressed by advocates and healthcare providers," Haynes said.

The transition to managed care has been met with consistent complaints from both patients and providers, despite efforts of the cabinet to work through the issues and keep the channels of communication open between providers, the cabinet and the managed-care organizations.

Two passionately debated bills in the recent legislative session challenged some practices of the current MCOs: one seeking an appeals process for denial of payments and the other removing a cap of "triage fees" for emergency-room services that MCOs later deem not to be emergencies.

Both issues have been challenging to the financial health of rural hospitals. State Auditor Adam Edelen addressed many such issues in a recent report on the financial health of rural hospitals.

“We are pleased to see the cabinet taking steps to improve and strengthen managed care contracts, many of which we recommended in our recent report on the financial strength of rural hospitals,”Edelen told Insider Louisville.

Some requirements for the new contracts include: required statewide coverage; standardized rules among the MCOs; improved administrative processes; increased oversight of claim denials; continued expansion of behavioral health services; incentives for MCOs to work with Medicaid patients to decrease emergency-room use and improve their health; and increased penalties to assure contract compliance. Click here for the Cabinet for Health and Family Services' complete Request for Proposal.

“I’d like to say that they heard the voice of the people,” Schuster told Insider Louisville.“If you look at the Medicaid Advisory Council, those meeting are every two months and it’s the same litany of complaints and concerns every darned time with no response. The only thing I can think of is it’s a gesture by this outgoing administration to get things right so that regardless of who comes in next year, there are strong contracts in place. I applaud them for it, and I’m stunned.”

The current contracts with Anthem, Aetna's Coventry Cares, Humana's CareSource , Passport and Wellcare expire on June 30, 2015 and proposals for the new contracts are due by May 5. The statewide contracts will be awarded to multiple MCOs for a one-year period with four, one-year renewal option, according to the news release.

Sunday, April 5, 2015

Auditor will hold meetings in Prestonsburg, Princeton and Sonerset to discuss his report on financial status of rural hospitals

State Auditor Adam Edelen will hold three public meetings in rural communities to discuss the findings of his special report about the financial health of rural hospitals.

The meetings will be held Monday, April 21 at 1 p.m. at the Mountain Arts Center in Prestonsburg; Monday, May 4 at 11 a.m. (CT) at the Caldwell County Memorial Hospital in Princeton; and Thursday, May 6 at 1 p.m. at the Liberty center of Somerset Community College.

The report, which covers fiscal years 2011 through 2013, found that as many as one-third of Kentucky's rural hospitals were in poor financial shape, with 68 percent of them ranking below the national average financially.

“Although closure may be an unfortunate reality for some," Edelen said in the press conference, "I believe more can and should be done to help these hospitals rethink their models of business in delivering health care in the 21st century." He went on to suggest rural hospitals consider hiring outside managers, merge with larger hospitals, form coalitions with other rural hospitals or find a specialized health niche as possible alternate business models to consider.

The report calls for the creation of a state work group to monitor rural hospitals, including making sure state law gives them the flexibility to retool their business models. Susan Zepeda, president and CEO of the Foundation for a Healthy Kentucky, suggested that the proposed work "could be incorporated into the work already under way under a State Innovation Model grant, which is engaging many sectors of health service in Kentucky in an ambitious, collaborative redesign effort."

Edelen said some of the primary problems faced by rural hospitals stem from the many changes in health care since the inception of Medicaid managed care, a decrease in the number of health-care providers, and an economic climate in some areas that doesn't support the current health payment model, which depends on the majority of its users to have private health insurance.

The report suggested that the Cabinet for Health and Family Services negotiate better contracts with managed-care organizations as it approaches the June 30 deadline, especially to address provider payments, stricter penalties for non-compliance and increased administrative burdens that managed care has put on hospitals. Edelen and Haynes sounded hopeful that this was going to happen.

Gov. Steve Beshear called Edelen's report "a dated snapshot" because the 2013 data used in the report does not include 2014 information,when the federal health reform was fully implemented through expansion of Medicaid to people with incomes up to 138 percent of the federal poverty line. Beshear said hospitals received $506 million to care for such people in 2014 while seeing significant reductions in losses on patients who couldn't or wouldn't pay.

Edelen's spokeswoman, Stephenie Hoelscher, said in an email that Edelen believes the full effect of all the changes in health care to hospitals' bottom line is still not clear, and his report establishes a baseline for critical analysis going forward.

Monday, March 30, 2015

Up to 1/3 of rural hospitals in poor financial shape, auditor finds, calling report a baseline for local decisions that could be tough

By Melissa Patrick and Al Cross
Kentucky Health News
For a video of Edelen's press conference, click here. For a cn|2 report with video, go here.

FRANKFORT, Ky. -- As many as one-third of Kentucky's rural hospitals are in poor financial shape, and the survival of some will likely depend on their willingness to adopt new business models, state Auditor Adam Edelen said Monday.

Unveiling a nine-month study, Edelen said 15 of the 44 hospitals examined were in "poor financial health," and warned, "Closure may be an unfortunate reality for some."
Rural hospitals in purple declined to make useful financial information available to the auditor's office.
The study did not include 22 of the 66 Kentucky hospitals that are located outside metropolitan areas, which declined to participate or didn't provide the type of information requested. Edelen said those hospitals are mainly privately owned. If they had been included, Kentucky Hospital Association CEO Michael Rust said, the financial picture "would be better, but I don't think they would be substantially different."

Gov. Steve Beshear said the report was "a dated snapshot" because its most recent data was from 2013, before federal health reform was fully implemented. "Conditions are no longer the same," Beshear said in a news release. "Hospitals received more than $506 million in 2014 through new Medicaid expansion payments, while seeing significant reductions in uncompensated care costs.  Those are huge changes to hospitals’ bottom lines that are not shown here."

Edelen, who was Beshear's first chief of staff, said the full effect of federal health reform isn't certain. His report noted that Kentucky hospitals have had higher-than-average penalties from Medicare for readmitting patients within 30 days, a newly implemented feature of the law. Forty of the 63 hospitals penalized were rural, and nine of the 39 in the U.S. that got the maximum penalty were in Kentucky.

"This report doesn't speak to causation" by the reform law or the state's relatively new managed-care system for Medicaid, Edelen said, it is "not a rebuke" of either, but provides "a baseline for monitoring" by policymakers at the state and local levels.

The report says that to survive, rural hospitals must adapt to new business models, such as merging with larger hospitals or hiring them as managers, forming coalitions with other rural hospitals, or finding a health-care niche that hasn't been served.

Edelen cited Rockcastle Regional Hospital, which has become a niche provider of ventilator dependent care and the coalition formed by Morehead's St. Claire Regional Medical Center and Highlands Regional Hospital in Paintsville to provide more efficient care, improve patient access and adapt to changes under the reform law.

Adaptations might be a hard pill to swallow for many rural hospitals because they call for yet more change in the rapidly changing health-care landscape of electronic health records, managed care, Medicaid expansion and full implementation of the Patient Protection and Affordable Care Act.

Edelen said adaptation is important for rural communities, for whom "the importance of rural hospitals cannot be understated. They provide health care to 45 percent of Kentuckians and in every community they serve they act as one of the larger employers, paying a significantly higher wage than the average the community experiences."

He also cited the many small hospitals that have formed relationships with larger networks to relieve the increased administrative burden associated with the three-year-old managed-care system. The report says half the hospitals studied have reported an increase in hours spent on administration.

The report suggested that the state Cabinet for Health and Family Services negotiate better contracts with managed-care organizations, partly to streamline MCO rules and paperwork to reduce the administrative burden. "We are optimistic that the current work of the cabinet to improve those contracts is going to bear real fruit," Edelen said.

The new contracts will start July 1. In an interview, cabinet Secretary Audrey Haynes sounded optimistic about them but said she couldn't give details.

Haynes has been saying since she became secretary three years ago that many hospitals must change the way they do business. She said in an interview that the readmission penalties have forced hospitals to change by providing better discharge planning, and utilizing outpatient services like home health, nursing homes and rehabilitation.

One Kentucky hospital, in Nicholas County, has closed in the last year. Haynes said the cabinet is working with Fulton County, whose hospital is scheduled to close March 31, to explore how to continue providing care at the facility, such as an emergency room or an ambulatory surgical center.

Haynes recommended in the interview that all nonprofit hospitals put audited financial records and their tax returns on their websites and adhere to open-meeting laws.

In a lengthy response, included in the report, Haynes rejected Edelen's suggestion that her cabinet regularly monitor the fiscal strength of rural hospitals. She said in the interview that would pose a conflict of interest, since the cabinet regulates the hospitals.

Edelen's analysis of hospitals' financial health was based on percentage of revenue kept as profit, number of days of cash on hand, debt financing and depreciation. It found that the financial condition of 68 percent of Kentucky’s rural hospitals scored below the national average.

Edelen's office also surveyed rural hospital administrators, held 11 public hearings and met with representatives of all five Medicaid managed-care companies. His report found that:
  • Rural hospitals that were geographically well-positioned, such as Pikeville Medical Center, scored high while geographically-isolated hospitals, like those in Clinton and Wayne counties, scored low. The Clinton County Hospital is in bankruptcy to restructure debt incurred for an expansion and modernization.
  • The Pikeville hospital, formerly Pikeville Methodist, was one of only three judged to be in excellent financial health. The others were critical-access hospitals in Franklin and Morganfield.
  • Critical-access hospitals, which limit their beds, services and patient stays to qualify for federal reimbursement at 101 percent of cost, scored better than regular acute-care hospitals. They accounted for seven of the 14 that were above the national average and thus were rated "good."
  • Fifteen hospitals were rated "fair" and 15 were rated "poor." Westlake Regional Hospital in Columbia, which is in bankruptcy, was at the bottom, far worse than the next highest, St. Joseph Mount Sterling.
  • The number of health-care providers across the state – particularly in rural Kentucky – dropped significantly between 2013 and 2014. The cabinet disputed that finding, based on different measurements.
Here are the rankings (click on the image for a slightly larger version):

Sunday, March 29, 2015

Kentucky is one of three states to get Walmart Foundation money to expand farm-to-school programs

Kentucky will use money from The Walmart Foundation to partner with the National Farm to School Network to expand efforts to get more local foods into schools.

A project called Seed Change will “jump start” programs that get local foods into schools and enhance food education for more than 1.8 million school children at 100 sites in Kentucky, Louisiana and Pennsylvania, the network said in a news release. Each site will get $5,000 grants, with applications to be accepted later this spring.

The state Department of Agriculture’s farm-to-school program connects schools with local farmers and food producers and helps students "learn to appreciate the importance of local foods and grow into well-informed consumers who demand local foods as adults," the release said. The program served an estimated 364,000 children in about 700 schools in 84 districts in the 2011-12 school year. For more information on the program, go to www.kyagr.com or contact Tina Garland at 502-382-7505 or tina.garland@ky.gov.

Tuesday, March 17, 2015

Health foundation says consumers need price transparency; Medicaid health officer says some commercial interests want it

Kentucky Health News

The Foundation for a Healthy Kentucky says a major step needed to improve the health of Kentuckians is transparency of their health-care cost and quality.

"Consumers can (then) compare apples to apples," Susan Zepeda, the Foundation's president and CEO, told Greg Stotelmyer of Public News Service. "What is a particular procedure going to cost if I have it at this hospital versus that outpatient surgery center? What are my co-pays going to be or my deductibles under my insurance plan?"

The foundation recently recommended that Kentucky develop and establish an all-payer claims database, or APCD, for consumers and stakeholders as a tool for transparency. John Langefeld, chief medical officer of the state's Department of Medicaid Services, told Stotelmyer that "support for the idea is growing, including from many on the commercial side of health care."

But this type of transparency is not likely to happen without a law to require it, which Kentucky does not have, Stotelmyer reports.

Massachusetts is the only state that requires the type of health-care transparency the foundation is talking about. And while it is not a perfect system, with reported prices not reflecting all of the involved charges, frequent price changes and weak information about the quality of care, it is still "unlike anything else in the country," Martha Bebinger reports for Kaiser Health News.

Oregon could possibly become the second state to require health-care transparency. Two bills for it are pending in the current legislative session. One that would require hospitals to reveal their median prices for common inpatient and outpatient procedures, "is expected to get very little opposition as it makes its way through the legislative session," Chris Willis reports for KGW in Portland.

But physician and system theorist Deane Waldman argues in the Huffington Post that price transparency won't work. She says that transparency can't reflect the real cost of health-care, doesn't reflect health outcomes or quality of care, and when it does reflect outcomes, it only reflects the average outcome and not individual probabilities. She also says that because the current health-care in the U.S. is not a free market, consumers have no reason to economize.

The Foundation for a Healthy Kentucky disagrees. "Sunshine on pricing will make sure that we're all playing by the same rules," Zepeda told Stotelmyer. Kentucky has the ability to gather the data, but it still needs "the political will" to do so, she said.

Thursday, March 5, 2015

State Senate passes bill for independent appeals process for managed-care claims; hearing gets into details of the problem

By Melissa Patrick
Kentucky Health News

Managed-care organizations' contracts allow them to deny Medicaid claims and not reimburse for services if they deem them not medically necessary. That means health-care providers often don't get paid for providing care, and their only recourse is an internal review by the MCO.

Sen. Ralph Alvarado
"It appears some of our MCOs are using this denial method in order to, as they term it, 'manage care'," Republican Sen. Ralph Alvarado said at a Senate Health and Welfare Committee hearing on his Senate Bill 120, which would set up an independent appeals process for providers, much like those in Georgia and Virginia.

The  bill, which had been in the works for several years, passed the Senate March 2 and was received in the House March 3. Its prospects in the House appear poor because it is opposed by the Cabinet for Health and Family Services, which oversees Medicaid. Its main targets are MCOs WellCare of Kentucky and Coventry Cares of Kentucky.

Alvarado, a Winchester physician, said in an interview that he pointed out these companies because they have the highest denial rates. While other companies also have complaints, "They are very small and minor, what you would expect in the normal course of business," he said. "It is WellCare and Coventry; these two are the names that keep coming up over and over again."

Asked for comment, Coventry said in an e-mail, "Coventry continues to monitor the legislation as it moves through the process. We are working with lawmakers to protect the integrity of the managed Medicaid program and be responsible with taxpayer dollars."

WellCare said in an e-mail that its appeals process is adequate, offering two additional remediation alternatives, negotiation and arbitration. The company said MCOs are "continuously subjected to rigorous oversight by state, federal and national accreditation entities," which ensure that they "adhere to strict standards and evidence-based guidelines in determining medical necessity."

Nina Eisner, board member of the Kentucky Hospital Association and chair of its Chemical Dependency Treatment Program, told the committee that providers deserve the same sort of state appeals process that patients have for denial of service.

"Kentucky's providers are under tremendous pressure from payment cuts from Medicare and slowed and denied payments by MCOs," Eisner said. "It is untenable and unreasonable to expect that Kentucky providers can provide health care services for free."

She said that many of the disputes stem from MCO reviews using out-of-state physicians who "don't always understand the rural nature of our state and the lack of resources." She said one example is discharging rural patients from inpatient to outpatient behavioral-health or substance-abuse treatment where no outpatient services are easily acessible.

"The MCOs in Kentucky are quite profitable," Eisner said, citing a November analysis by Citi Research that found Kentucky's MCO plans generated over $450 million in earnings before interest, taxes and depreciation from the state Medicaid program. "This is a margin of 10.6 percent, which is more than two times the 3 to 5 percent margin most Medicaid plans target."

Sen. David Givens, R-Greensburg, said he was compelled to remind those at the hearing that private companies need to be profitable to keep the system working. Later, Sen. Danny Carroll, R-Paducah, disagreed, saying MCOs' profits need to be more balanced.

Medicaid Commissioner Lisa Lee said that it is balanced, because MCOs were required to spend 87 percent of their payments on the population newly eligible for Medicaid or give it back to the federal government, and that rates going forward depend on what they spend today.

KHA's Nancy Galvagni said another reason for a state appeals process is the variation between plans' denial rates, ranging from a low of 7 percent to a high of 18 percent. She said that providers have gone to state hearings on behalf of their patients and had favorable opinions, only to have them overturned by the Cabinet.

Tina Heavrin, general counsel for the cabinet, said that occurs because the cabinet only has authority to decide whether patients received services, and if they did, there is no claim and any dispute regarding payment is between the MCO and the health-care provider.

Sen. Julie Raque Adams, the committee chair, replied, "I think that is the impetus behind this bill, that once the patient receives their service, they are done, but the provider is not. ... I don't want to go to work and not be paid for it. And I don't think that is an unreasonable thing to request or require and I think that is all that this bill does."

Heavrin said that providers do have a process to resolve these issues, "It is called the judiciary." She said the cabinet can't run an appeals process for MCOs because it "as part of the executive branch, doesn't have jurisdiction or legal authority over an adjudication of private contract rights." She added, "The MCOs are our contractors and it would be difficult to not have a financial interest in the outcomes of those appeals," meaning that upholding an appeal would cost the state money.

Lee said the cabinet acknowledges issues with MCOs. She said that while state officials should not get in the middle of contract disputes, "We do listen to our providers" and "want to hold our MCOs accountable," noting that they had "made some significant progress with managed care" since its inception in 2011.

Carroll, who deals daily with MCOs through his non-profit agency that provides therapy services and medical-based child care, said, "It is an absolute nightmare dealing with MCOs," because of all the "hoops to jump through in order to get reimbursement."

He asked if there was any way for the cabinet to work these issues out in its new contracts and said it felt like the state had "brought in these MCOs and basically washed their hands of all the issues associated with it."

Heavrin said it would not be possible to include a state appeals process in the contracts because "We can't be a judiciary."

Lee told Carroll that state officials had not "washed their hands" of the MCOs and closely monitor their activities. "We also have an obligation to the Center for Medicare and Medicaid Services to make sure that every single thing that we pay for does meet medical necessity," she said. CMS is the federal agency that oversees those programs.

Saturday, February 28, 2015

Beshear says Ky. rural hospitals 'have a positive cash flow' but he can't prove it; industry says it sees 'some improvement'

By Al Cross
Kentucky Health News

FRANKFORT, Ky. -- Gov. Steve Beshear says Kentucky's rural hospitals are profitable again, thanks to his expansion of Medicaid, but he offers little evidence to support his claim, and the hospital industry disputes it.

In a long, joint interview with Colorado Gov. John Hickenlooper at the Brookings Institution in Washington, D.C., Feb. 20, Beshear said, “Our rural hospitals have a positive cash flow for the first time in a long time, so it’s working, it’s going to work, and my job is just to get it so embedded that nobody can do anything about it.”

Kentucky Health News asked Beshear's office for evidence of rural Kentucky hospitals’ positive cash flow, but the office cited only a news story about Carroll County Memorial Hospital in Carrollton, which said it turned a small profit in 2013 (thanks to federal health-reform grants for digitizing medical records) and a much larger one in 2014.

"Some of them have improved and some of them have not," said Mike Rust, president of the Kentucky Hospital Association. As a result of Medicaid expansion, he said, "Some have benefited greatly but others are still struggling."

The association's vice president of health policy, Elizabeth Cobb, said, "In general we’re seeing some improvement in rural hospital finances," largely from a decline in the number of charity cases as a result of previous patients having coverage. "We were already taking care of most of those," she said.

State figures show Medicaid payments to rural hospitals rose 20 percent in the state fiscal year that ended June 30, 2013, but only 6 percent in the next year, when the Medicaid expansion began; and that the payments to urban hospitals rose 4 percent and 10 percent the last two years.

Based on claims from July through September, the state forecasts that Medicaid payments to rural hospitals in the current fiscal year will increase 26 percent, and payments to urban hospitals will rise 15 percent. (The state has estimates for each hospital.)

Cobb said the expansion hasn't generated as many new patients as might be expected for rural hospitals because of the shortage of primary-care physicians who admit patients: "We're not seeing a huge expansion of utilization as a result of Medicaid expansion."

That keeps patients coming to hospital emergency rooms for care, some of which is deemed non-emergency by managed-care organizations, the insurance-company subsidiaries that have overseen the care of Medicaid beneficiaries since 2011. Two MCOs pay only a $50 "triage fee" in such cases, regardless of what diagnostic tests the hospital performs; that was the topic of a legislative hearing last week.

And that is just one part of hospitals' problems with the MCOs. "What we're seeing generally is that while hospitals are receiving payment for some patients who may have been uninsured previously and are now insured by Medicaid, we're still seeing the challenges of hospitals being paid by managed-care organizations," Cobb said. "There's an increase in the administrative burden for small hospitals to work with five different MCO plans that all have very different rules and criteria."

Clinton County Hospital Administrator J.D. Mullins cited MCO problems is explaining his facility's decision to file for bankruptcy last year, mainly to restructure payments on the federal loan for a $14.7 million addition completed a few years ago, the Clinton County News reported.

"These companies’ polices have restricted access to the hospital’s services and reduced our reimbursement even more," Mullins told the Albany paper. "When the idea of a new hospital facility was first proposed, no one could have foreseen the condition of health care today."

The hospital is in the district of Sen. Max Wise, R-Campbellsville, who told fellow members of the Senate Health and Welfare Committee Feb. 26, "I would love to take the governor's report to the six of my seven counties out in rural Kentucky that are struggling right now in their hospitals. . . . What I'm hearing from them is the system is broken and it continues to be broken."

Wsie was referring to Beshear's recent report that Medicaid expansion is generating more money, jobs and tax revenue than forecast. Another committee member, Sen. Ralph Alvarado, R-Winchester, said, "Almost every senator here has received letters that say: This stinks, we are not getting paid, we are going under."

Cobb said some rural hospitals are reporting cuts in jobs and services. That is probably reflected in U.S. Bureau of Labor Statistics data compiled by Paul Coomes, emeritus economics professor at the University of Louisville. It shows hospital employment trending down while other health-care jobs have been going up.

While Carroll County and others are benefiting from federal digitization grants, "That funding’s going to go away," Cobb said, and "Every year you've got to pay for upgrades, and the requirements continue to increase at the federal level." Federal officials say digitization should make hospitals more efficient.

Of the Carrollton hospital, Cobb said, "That’s a special situation. That’s not a typical one." She said the facility "put in place a lot of measures to try to improve their management" and has partnered with larger hospitals to offer more services, such as cardiology, "and that’s breathed some life back in."

Rural hospitals in Nicholas and Fulton counties have closed in the last year, and state Auditor Adam Edelen, who is preparing to issue a report on rural hospitals, has warned that others are in danger, threatening to put new obstacles between rural Kentuckians and health care. "Not acknowledging the looming access issue is a disservice to the low-income and elderly Kentuckians who are depending on an intact provider network,” Edelen spokeswoman Stephenie Hoelscher said.

Friday, February 27, 2015

Bill would require Medicaid managed-care firms to pay contracted fees for ER visits; Senate hearing targets two companies

This story has been updated with comments from Wellcare of Kentucky.

By Melissa Patrick
Kentucky Health News

FRANKFORT, Ky. -- Managed care is touted as a way to achieve value-based care in the Medicaid program, but hospital emergency rooms in Kentucky aren't finding much value in not being paid the contracted price for their services by two of the managed care organizations.

Officials of two Kentucky hospitals told the Senate Health and Welfare Committee Feb. 25 that Wellcare of Kentucky and CoventryCares of Kentucky are denying payment for as many as half of their emergency-room patients who seek care in their facilities, reimbursing the hospital a flat $50 "triage fee," less the patient's $8 co-payment, regardless of diagnostic tests performed in the ER.

Cheri Sibley, CEO of Clark Regional Medical Center in Winchester, noted that emergency rooms are required by law to screen patients with appropriate diagnostic tests to rule out an emergency condition if they come to the emergency room and ask for care.

Wellcare and Coventry are two of the five Medicaid managed-care organizations that oversee care for the state.

Wellcare said in an e-mail that it is required by the Department of Medicaid Services to "have an affirmative program to address the high cost of emergency room treatment for conditions that do not require this level of care." The company said the triage fee is just one measure it has taken; it said an "emergency room prudent layperson program" has helped "identify and sometimes prevent payments as much as 500 percent to 1,300 percent more in an emergency room as compared to a physicians office for common ailments such as ear aches and sore throats."

Sen. Ralph Alvarado, a physician from Winchester, has sponsored a bill that would require MCOs to pay the previously negotiated rate for emergency-room examinations and allow the ER doctor to determine whether a patient's condition is an emergency or not,.

"This bill is an attempt to keep our Medicaid managed-care organizations accountable," Alvarado said at the meeting. "MCOs have been shortchanging our providers and our hospitals -- and, I would argue, purposefully -- for the past three years. . . . MCOs are basically managing health-care cost by non-payments to providers."

Since the advent of managed care in 2011, hospitals have complained about late and denied payments and difficulty dealing with MCOs. "The problem has reached critical mass, threatening the survival and financial viability of our hospitals, and almost every legislature has been contacted by their local hospital provider regarding these (issues)," Alvarado said.

Kentucky implemented managed care as a way to save money. Basically, insurance company subsidiaries get a certain sum per patient and increase their profits by controlling costs. The Cabinet for Health and Family Services maintains that managed care focuses on quality and provides better accountability for care as opposed to the traditional fee-for-service model, but provider complaints about slow payments and rejections of claims have persisted since its inception.

Hospitals bill insurance and Medicaid based on the level of complexity of emergency-room care provided based on the symptoms the patient presents, regardless of the final diagnosis. Payment has typically been based on a fee that was pre-negotiated between the hospital and the MCO.

Wellcare and Coventry have since implemented a non-negotiated "triage policy," which allows these organizations to determine, after the fact, whether a patient had an emergency. If they determine that a patient was a non-emergency, regardless of presenting symptoms and cost of diagnostic procedures (X-rays, CT scans, lab tests, and so on), they only pay $50 minus the $8 co-payment, or $42. Wellcare implemented this policy in September 2012 and Coventry in April 2013.

The legislaure's Administrative Regulation Review Subcommittee found last May that the triage policies did not follow federal standards, according to Sibley and Alvarado.

"One side seems to be meeting their contractual obligation, while the other side seems to be deficient in meeting their contractual obligations," said Sen. Julie Raque Adams, R-Louisville, chair of the committee.

Hospitals can appeal MCOs' decisions, but "hospitals report that only a small number of these are overturned with no explanation of decision given," Sibley said.

Sibley gave an example of a claim that had been determined a non-emergency by one of these companies at her hospital: An 18-month-old girl was brought to the ER because she was blue in color, wheezing and short of breath. She had an X-ray, other diagnostic tests and a breathing treatment, but the hospital was paid $42 by the MCO plus the $8 co-payment, if the patient paid it.

"The two MCOs in question should not be deciding which patients are non-emergencies," Sibley said. "They should be abiding by their negotiated contract and paying the contract rate," 95 percent of allowed cost.

Sibley presented Kentucky Hospital Association data from 64 hospitals affected by these triage policies. The report found that during calendar year 2014, the hospitals reported submitting nearly 380,000 emergency room claims to Wellcare and Coventry, of which 140,000 were denied except for the $50 fee. The overall denial rate was about 37 percent; Wellcare's was 48 percent.

The KHA report said the difference in the flat fee and the contracted rate totaled $37.4 million, and that the more complex visits (and this likely the more expensive) were the ones most often denied payment.

"With one in four Kentuckians now on Medicaid, this problem is only going to get worse, if this is not corrected by this Senate Bill 88," Alvarado's legislation, Sibley said.

Georgetown Community Hospital CEO William Haugh said almost 30 percent of its ER visits in 2014 were Coventry or Wellcare clients. Wellcare classified almost 60 percent as triage cases and paid only $50 each. The hospital appealed 92 percent of those cases, with a success rate of 16 percent, or 285 patient encounters. Haugh said that amounted to a $334,258 underpayment, plus an estimated $40,000 cost for preparing and prosecuting the appeals.

Haugh said Coventry classified 26.4 percent of its clients' Georgetown ER visits as triage and paid only $50 each. The hospital appealed 94 percent of those and had a success rate of 36 percent, or 366 patient encounters. He estimated an underpayment of $148,000 plus $22,000 in labor for appeals, and said the overall financial impact to the hospital was $543,894.

Wellcare said its appeals process allows three opportunities for review, with at least two independent medical directors.

The state Medicaid program's chief medical officer, Dr. John Langefeld, said the emergency-room problems are not a "straightforward, easy issue," He said many patients go to ERs for reasons beyond medical care. The cabinet has said that some hospitals have relied too much on ER revenues.

Sen. Reginald Thomas, D-Lexington, said rural hospitals need to change their business models and wondered if the bill was an attempt to mask that problem. Meanwhile, he added later, there is "documentation that hospitals have benefited from Medicaid expansion" under the federal Patient Protection and Affordable Care Act, in a recent report from Gov. Steve Beshear.

Adams replied that Beshear says, ""It is great, and it's putting all this money back in the system," but in fact we are not seeing it on the provider level."

Alvarado said, "There is a difference between what actually happens and what the governor's office wants to show you. So when you have KentuckyOne [Health] coming out publicly declaring a $218 million dollar loss in one year, that is hardly a profitability for them based on the ACA."

Alvarado said Citibank reported the companies have made $155 million in profits off of Kentucky Medicaid. "I'd get rich, too, if I didn't pay my bills," Alvarado said. "It is an outrage."

Sunday, February 22, 2015

UK gets approval to add 120 hospital beds, bringing its total to 945 and long-term building project's cost past $1 billion

The University of Kentucky has received state approval to add 120 beds to its hospital complex, which will bring its total to 945 beds at UK Chandler Hospital, Kentucky Children’s Hospital and UK Good Samaritan Hospital.

The project is "part of the overall strategy to make UK the regional hospital of choice among several states and a powerhouse that will survive when health care is so uncertain," Lexington Herald-Leader higher-education reporter Linda Blackford said Friday on KET's "Comment on Kentucky."

Dr. Michael Karpf
Blackford writes for the newspaper, "The 120 beds are the next phase in the patient tower project that began in 2004 with an estimated cost of $400 million and an original completion date of 2009. The cost of the expansion has risen to roughly $1 billion, and there is no longer a completion date, said Dr. Michael Karpf, executive vice president for health affairs at UK. After the 120 beds are added, the tower still will have several empty floors.

"The shifting timetables are all a part of coping with a fast-growing patient base and ever-changing medical technology, Karpf said. Originally, the patient tower was to be a replacement for Chandler Hospital, which was built in the 1950s. But a rapid increase in the number of patients meant the space now will be used for new beds, he said."

Read more here: http://www.kentucky.com/2015/02/19/3703219_state-approves-uk-hospital-expansion.html?rh=1#storylink=cpy

Karpf said in a UK news release, "About 10 years ago, we committed to develop UK HealthCare into a research intensive, referral academic medical center to ensure all Kentuckians — no matter how complex their medical problem — could be taken care of in Kentucky and not required to leave the state for advanced subspecialty medical care," said Karpf. "This strategy, while crucial to our goal of taking care of patients in the commonwealth, has resulted in substantial growth beyond our initial aggressive projections."

Wednesday, February 18, 2015

Opinion: Toward a healthier Kentucky, with a smoke-free law

By the Friedell Committee for Health System Transformation 
It is no secret that Kentucky is among the unhealthiest states in our country. 
Kentucky is No. 7 in cardiovascular deaths, No. 1 in cancer deaths, No. 1 in lung cancer, and No. 13 in asthma prevalence. And Kentucky leads the nation in smoking with 26.5 percent of its adult population.
Even non-smokers are at risk of diseases caused by tobacco. Exposure to secondhand smoke increases the risk of coronary heart disease by 25 to 30 percent among nonsmokers.  It increases the risk of lung cancer in nonsmokers by 20 to 30 percent. 
This means that waitresses and bartenders (most of whom do not smoke) in workplaces that allow smoking risk their lives just to earn a paycheck.  Sadly, 68 percent of Kentuckians are currently exposed to secondhand smoke in public places.  At this rate it is no wonder that Kentuckians suffer serious and deadly consequences.
Fortunately, we have scientific evidence that a smoke-free law will reduce disease rates in areas where such a law is in effect. Communities that pass comprehensive smoke-free workplace laws have experienced a 15 percent drop in emergency-room visits for heart attacks.  ER visits for asthma dropped by 22 percent in Lexington after the smoke-free law was enacted. 
Also, adult smoking rates declined by 32 percent in Lexington, saving $21 million per year in health care costs! While a decrease in smoking rates is not the primary reason for secondhand smoke-free laws, many people express an interest in stopping, and the laws make quitting easier.
Our poor health is a problem that affects us all.  It affects our health-care costs, our community health, and a national perception of us as being an unhealthy place to invest in and live.  That problem can be addressed by smoke-free local ordinances, a state law, and/or local boards of health regulations. 
The Affordable Care Act presents a unique opportunity to look at health differently.  We need to start emphasizing prevention of diseases rather than relying only on treatment.  Smoke-free policy is one effective type of prevention. We know that prevention will save lives and reduce health care costs borne by individuals, private business and the government. 
The Saving Our Appalachian Region effort in Eastern Kentucky reminds us that Kentucky can do better.  Going smoke-free is one way. Imagine a Kentucky where no one is exposed to smoke in the workplace and where fewer people actually smoke.  Lives would be saved, diseases would be prevented, and health care costs would decrease.
Thankfully, most Kentuckians agree. Statewide polls show that 66 percent of likely voters are in favor of a smoke-free law.  This makes sense since most Kentuckians do not smoke.  It is time for the state legislature to implement a policy that will improve our health, save lives and reduce health costs.
The Friedell Committee for Health SystemTransformation is an organization of community leaders across the state that knows that Kentucky is not a healthy state but that working together we can do something about it.

Sunday, February 15, 2015

'Medicaid Dashboard' gives county-by-county details on 375,000 who joined program, what screenings they got, what they found

The expansion of the federal-state Medicaid program under federal health reform marks the biggest change in Kentucky health care since Medicare began in the mid-1960s. Almost 400,000 people have joined the program, raising its rolls to more than one-fourth of the state's population. This is an important story in almost every county, and the state has the data to tell it.

As part of the $141,000 study of the first year of Medicaid expansion, Deloitte Consulting created for the state and its citizens a "Medicaid Dashboard" that gives detailed information about the newly eligible Medicaid enrollees in every county, by age, gender and chronic health conditions, along with information about payments to health-care providers in each county. Here's a partial screenshot, with one county highlighted:
And here's an example of how data from that county can be broken down by age and gender:
In addition to these data, and detailed information about payments to providers, the dashboard also reveals how many new Medicaid enrollees have been diagnosed with what chronic conditions, and what screenings and other preventive services they have received. This can also be broken down by county. For the dashboard, go here.
The data are only for people who were made eligible for Medicaid by the expansion, which raised the income limit to 138 percent of the federal poverty line, from 69 percent. The data do not include several thousand people who had been eligible for Medicaid under the old limit but did not enroll until the limit was raised.

Thursday, February 12, 2015

Highly anticipated report on first year of Medicaid expansion says Kentucky can afford it even with higher-than-expected enrollment


By Melissa Patrick
Kentucky Health News

FRANKFORT, Ky. -- Kentucky's decision to expand Medicaid under federal health reform is a better deal than previously projected and will more than pay for itself, Gov. Steve Beshear said as he unveiled a top consulting and accounting firm's study of the expansion's first year and projections for the next seven.

"For all the naysayers who claimed that expanding Medicaid was a budget-busting boondoggle, take a look at the facts. It's working, and it's literally paying off. The state is saving money, hospitals are earning more, and our people are getting healthier," Beshear said.

The report was conducted by Deloitte Consulting and the University of Louisville's Urban Studies Institute and cost $140,000, which was paid from Medicaid's administrative budget, half state funds and half federal.

Beshear said a study from Deloitte is "about as reliable as any study can be" and conclusively, with "an avalanche of facts," informs the critics that Kentucky can afford to pay for Medicaid expansion.

"Kentucky can indeed take care of its people, In fact, we can't afford not to do so," he said.

The report says that through 2021, Medicaid expansion will add 40,000 new jobs with an average annual salary of $41,000, putting $30 billion into the state's economy, and adding nearly $820 million to state and local budgets.

That, the report says, will cover the estimated cost of the matching funds that the state will have to pay for care of the newly eligible enrollees, those between 69 percent and 138 percent of the federal poverty level. The match will start at 5 percent of the cost in 2017 and rise to the law's cap of 10 percent in 2020.

For the next two budget years, from July 2016 to June 2018, the report estimates Kentucky will pay $74.4 million and $173.2 million, respectively. The report says this will be offset by $511.8 million of General Fund savings and tax revenues expected from the increased economic activity resulting from additional health care spending.

"These are conservative estimates," Beshear said, without any estimated savings from better health that he said will result from more people getting health care.

A Gallup poll released this summer said that Kentucky saw the second largest decrease of any state in its uninsured rate, dropping to 12 percent from 20 percent.

The study's projections were more favorable than those in a study by the PriceWaterhouseCoopers accounting and consulting firm, which Beshear cited when he announced in May 2013 that he would expand Medicaid. That study estimated the expansion would create 7,600 new jobs in 2014, but Beshear said the actual number was more than 12,000, including 5,400 in health care. Pricewaterhouse estimated 17,000 new jobs through 2021, well under Deloitte's forecast of more than 40,000.

Pricewaterhouse also underestimated the enrollment in Medicaid. In the first year, more than 375,000 people enrolled, about double the number that the firm estimated would enroll by 2020. That means the cost of the state's match will be higher than expected, but covered by jobs and taxes resulting from the higher enrollment.

“People can have whatever opinion they want, but they aren’t entitled to their own facts,” Beshear said. “It’s one thing just not to like [Medicaid expansion] because the president has his name on it, and if that’s the reason they want to take health care away from 500,000 Kentuckians, then that’s their opinion and people oughta know that. This report answers the questions, will it work, and yes it is working in Kentucky, and can we afford it, and yes we can."

The report is online at Governor.ky.gov. For county-by-county data, go to http://governor.ky.gov/healthierky/Documents/medicaid/Medicaid_Hospital_Report.pdf.

Wednesday, February 11, 2015

Sponsor of local opt-out amendment says smoking-ban bill needs it to pass; sponsor and House leaders don't care for it

By Melissa Patrick
Kentucky Health News

UPDATE: The House didn't vote on this amendment, but Sen. Jimmy Higdon, R-Lebanon, says it or something like it would give the bill a better chance of passing the Republican-controlled Senate.

FRANKFORT, Ky. – Rep. Steve Riggs of Louisville has proposed an amendment to the statewide smoking ban bill that would allow cities and counties to opt out of the ban every two years, saying he wants to improve the bill's chances of becoming law.

Riggs
“This amendment would negate a lot of concern about taking away local rights,” Riggs, a Democrat who supports the ban, said in a press release.

His Floor Amendment 9 to House Bill 145 proposes that local governments be able to opt out of the ban, but would be required to take another vote every two years to prevent the ban from taking effect in their jurisdiction.

Rep. Susan Westrom, five-year sponsor of the ban, first said she welcomes amendments because that is "how we edit our legislation," but still needed to talk to Riggs – and when asked if she thought this amendment was a good idea, she said it "goes against the intent of the bill."

"It is a little bit too late for this amendment," the Lexington Democrat said. "We have made too much progress."

House Speaker Greg Stumbo, who says he supports the bill but has clashed with Westrom about its handling, agreed. "I think if you started from day one with that as the idea," he said, "it might have been more palatable."

Stumbo and Republican Leader Jeff Hoover said the amendment would defeat the bill's purpose.

Hoover
Hoover noted, "Advocates have said for many years that we have to have a state-wide smoking ban because of the health concerns all across Kentucky."

Riggs said in an interview that the legislation hasn't had the votes for the past five years and it is time to do something different.

"If you keep swinging at the ball and missing time after time, you probably ought to change your stance," he said. "And that is what they need to do. They need to make a change to get more votes so it will pass."

Westrom said, "We have the votes." But House leaders told her Friday, Feb. 6, that she would need to have commitments from 55 of the 100 House members before they would bring her bill up for a vote.

"What it really says is, it takes 51 votes to pass, but we want 55 commitments because we can't trust everybody," Hoover said. "It's not about having a cushion; it's about they can't trust their own members when they say they are going to vote for something." He said Democratic leaders "should have the discipline to keep amendments, such as this one, from being filed."

Riggs said as chair of the House Local Government Committee, he is sensitive to the needs of cities and counties, and "If we give those people an option to opt out of it, we might be able to get some votes up here to pass the bill."

He said his amendment would allow the bill's advocates to get 90 to 95 percent of what they want to accomplish. "Most people consider that an A, excellent," he said. "This bill might bring in another 10 votes, because people feel if they have the option to opt out, that is liberty and freedom."

Riggs also said the idea might improve the bill's poor chances for passage in the Senate because some senators showed interest in the approach last year.

This is the right thing to do because they don't have enough votes to pass the bill in the House and the Senate," Riggs said.

He said smoke-free advocates don't want any changes to this bill and have not been willing to compromise for the past five years, and asked, "How much illness can we put at their feet because they won't change their swing?"

James Sharp of the American Cancer Society's lobbying arm, the Cancer Action Network, declined to comment.

Hoover, one of the relatively few Republicans for the bill, said he is mindful of opponents' arguments about personal property rights, but also of the "associated health risk with smoking and second hand smoke and the cost that this state is incurring in treating those folks who have diseases related to smoke and second hand smoke."

He concluded, "When I do the balancing test for me personally, I come down on the side that this is a step in the right direction to reduce health care cost and save lives."

Saturday, February 7, 2015

Panel OKs new medical-order form that would clearly define a person's end-of-life wishes on nutrition, hydration, medication

A bill to create a medical order form that details a person's wishes for end-of-life care passed the Senate Health and Welfare Committee Feb. 4 and seems headed for passage in the full Senate.

Advocates say that while many physicians discuss end-of-life care with their patients and families and document it, this information is often buried deep in the chart and is not easily accessible in an emergency situation.

"This issue comes to play on a daily basis," Christian Furman, vice-chair of geriatric medicine at the University of Louisville and medical director of two nursing homes in Louisville, told the committee.

Sen. Tom Buford
Senate Bill 77, sponsored by Sen. Tom Buford, R-Nicholasville, would creates a new Medical Order for Scope of Treatment form to specifically direct the type of treatment a patient would like to have and how much medical intervention they would like to have during end-of-life care. The MOST form is used in 32 states, Furman said.

The form is more detailed than a living will because it addresses not only the question of resuscitation, but specifies which life-saving measures, such as nutrition, hydration and medication, that a person wants to receive and under what circumstances.

The form must be reviewed annually. It allows for information sharing between providers and is part of the patient's electronic health record.

Furman said the order of controlling documents for end-of-life care is clearly defined in the bill: the living will first, the MOST form second, and the health-care surrogate, which is chosen by the patient and listed on the form, third.

Sen. Ralph Alvarado, R-Winchester, who is a physician, told his fellow committee members that the MOST form will not only assure a person's personal wishes are honored, but will also save an "immense" amount of money "just in terms of doing unnecessary treatments for folks."

"Five percent of Medicare beneficiaries die each year and their end-of-life care accounts for about 30 percent of total Medicare spending with as much as one-third spent in the last month of life," Bill First writes for Morning Consult, citing an article from the peer-reviewed journal Health Affairs.

Sen. Reggie Thomas, D-Lexington, a lawyer, said the medical community and patients need to be made aware that such forms exist. Buford said he trusted this would happen.

Friday, February 6, 2015

Feb. 15 is deadline to get health insurance; those who don't can be penalized up to 2 percent of their annual income

Sunday, Feb. 15 at 11:59 p.m. is the deadline to buy private, subsidized health insurance through Kynect, the state-run marketplace created under federal health reform.

If your annual income is above the federal poverty level and you don't buy a policy or enroll in Medicaid, and don't qualify for one of several narrow exceptions, you will be subject to a tax penalty from the Internal Revenue Service. (You may qualify for Medicaid if your income is less than 138 percent of the poverty level; Medicaid enrollment is open year-round.)

The penalty is $325 per person or 2 percent of household income, whichever is greater. "In many cases, this penalty could exceed the annual cost of insurance," the release said, giving these examples using "bronze" plans (the cheapest alternative, which has high deductibles):
  • A 30-year-old in Lexington making $20,000 would qualify for a subsidy and pay $37.44 for a full year of bronze coverage, or pay a $400 penalty and remain uninsured
  • A 25-year-old in Louisville making $40,000 would qualify for a subsidy and pay $604.08 for a full year of bronze coverage, or pay an $800 penalty and remain uninsured.
“Not only is insurance important for your physical health, it also makes financial sense,” Kynect Executive Director Carrie Banahan said in the release. “Why risk the possibility of being uninsured and facing a costly medical procedure and a tax penalty, especially when you may qualify for financial assistance to defray some of your premium cost? Don’t wait. Visit Kynect and enroll in healthcare coverage today.”

Private insurance on Kynect is subsidized by an advanced premium tax credit. Those who qualified for the credit will receive a 1095-A tax form, which provides information to help fill out Form 8962 as part of their federal tax returns. Individuals with questions about their Form 1095-A can call a special Kynect hotline at 1-844-373-2417. More information is available at kynect.ky.gov.

People on Medicaid, Medicare, the Kentucky Children's Health Insurance Program, catastrophic health insurance or insurance through an employer or other agency do not need Form 1095-A to file their federal taxes.

Thursday, February 5, 2015

Senate OKs bill for review panels in medical lawsuits after lively debate between doctors, lawyers, others

This story, which was published Thursday morning, has been updated with action in the full Senate.
By Melissa Patrick
Kentucky Health News

FRANKFORT, Ky. -- The Senate has approved a bill that advocates say will help weed out "frivolous" medical malpractice lawsuits and speed up litigation for legitimate suits.

Alvarado
"Right now, Kentucky has one of the nations most litigation-friendly environments, making our commonwealth a prime and profitable target for personal injury lawyers preying upon our health care providers," Sen. Ralph Alvarado, R-Winchester, a physician and sponsor of Senate Bill 6, told the Senate Health and Welfare Committee. Opponents disputed that claim.

The Senate passed the bill Thursday 24-12. It is not expected to pass the House.

The bill would establish panels of three medical experts, two chosen by each side and the third chosen by the other two, to review suits against health-care providers to determine if the case has merit before the lawsuit can proceed. Panel findings would be admissible in court but not legally binding.

The Republican-controlled Senate passed a very similar bill last year but it got nowhere in the Democrat-controlled House, and its prospects are similar this time. However, Wednesday's committee meeting provided a detailed and lively explication of the issue, lasing almost two hours.

Vanessa Cantley, a Louisville personal injury attorney, told the committee that most medical malpractice cases are legitimate. She cited a Harvard University study published in the New England Journal of Medicine that concluded "portraits of a malpractice system that is stricken with frivolous litigation are overblown" and reported that 97 percent of claims for medical injury evaluated over a decade were deemed to be meritorious.

However, Michael Sutton of Louisville, a civil defense attorney, said defendants win 80 per cent of medical malpractice suits.

Cantley said there are 2,700 deaths in Kentucky each year due to purely preventable medical error, but, according to the state Department of Insurance, fewer than 500 lawsuits a year are filed by abuse and neglect victims. She spoke for the Kentucky Justice Association, formerly the Kentucky Academy of Trial Attorneys.

Alvarado and other opponents argued that Kentucky has become a haven for such lawsuits and bills like his have helped deter them. "Medical review panels are a proven solution for limiting baseless claims brought by a personal injury lawyer to ensure a faster, more efficient path for patients with legitimate claims, " he said.

Alvarado said the state is 4,000 doctors short of its need and the legal climate in Kentucky makes it hard to recruit and retain doctors. Sen. Julie Raque Adams, R-Louisville, the committee chair, said the expansion of Medicaid in Kentucky makes it all the more important to make the state attractive to doctors. "Anytime there's a paradigm shift, there are other policies that  need to go along with that paradigm shift," she said.

Dave Adkisson, president and CEO of the Kentucky Chamber of Commerce, said review panels "will stabilize our medical malpractice system and make our state more attractive" and "protect the legitimate cases while weeding out the meritless claims," which increase costs to consumers and employers through higher premiums and defensive medicine in the form of extra medical tests.


Kentucky's constitution bans laws that would cap damages
in lawsuits. (Care First Kentucky graphic)
Every state surrounding Kentucky offers some level of protection against medical malpractice, while Kentucky offers no legal protections for healthcare providers, according to Care First Kentucky, a business coalition supporting the bill.

Sen. Reggie Thomas, D-Lexington, a lawyer, argued that Kentucky already has laws to punish attorneys for filing frivolous cases. Alvarado said the rule isn't used much because judges "allow a lot of latitude," and Sutton said it is reserved for "really egregious conduct."

Cantley argued, subtly, that courts are the refuge for patients who suffer from abuse, neglect and malpractice. She said the federal Centers for Medicare and Medicaid Services has ranked Kentucky No. 1 in nursing-home deficiencies, and argued that state boards that discipline doctors do a poor job.

The full Senate's debate on the bill was cut short because the committee adopted a substitute version, preventing Democratic Leader Ray Jones of Pikeville, a plaintiffs' lawyer, from offering any of his amendments, which had been drafted to the original bill. Under traditional procedures, a bill gets its required readings on days between the committee meeting and the floor vote, but in recent years Republicans have given important bills readings before committee action, allowing a vote on them the day after they pass a committee.